Rotten eggs, Rotorua and Parkinson’s disease

fixedw_large_4x

Being a proud kiwi, I am happy to highlight and support any research coming out of New Zealand.

Recently a new commentary has been published suggesting that living in the NZ city of Rotorua (‘Roto-Vegas‘ to the locals) may decrease the risk of developing Parkinson’s disease.

In today’s post, we will review the research behind the idea and discuss what it could mean for people with neurodegenerative conditions, like Parkinson’s disease.


iStock_000060169360_new_zealand_champagne_pool_rotorua

The geothermal wonderlands of Rotorua. Source: Audleytravel

Rotorua is a small city in the central eastern area of the North Island of New Zealand (Aotearoa in the indigenous Māori language).

The name Rotorua comes from the Māori language (‘roto’ meaning lake and rua meaning ‘two’). The full Māori name for the spot is actually Te Rotorua-nui-a-Kahumatamomoe. The early Māori chief and explorer Ihenga named it after his uncle Kahumatamomoe. But given that it was the second major lake found in Aotearoa (after lake Taupo in the centre of the North Island), the name that stuck was Rotorua or ‘Second lake’.

TAM-BLOG-1

Maori culture. Source: TamakiMaoriVillage

Similar to lake Taupo, Rotorua is a caldera resulting from an ancient volcanic eruption (approximately 240,000 years ago). The lake that now fills it is about 22 km (14 mi) in diameter.

p-8709-gns

Lake Rotorua. Source: Teara

The volcano may have disappeared, but the surrounding region is still full of geothermal activity (bubbling mud pools and geysers), providing the region with abundant renewable power and making the city a very popular tourist destination.
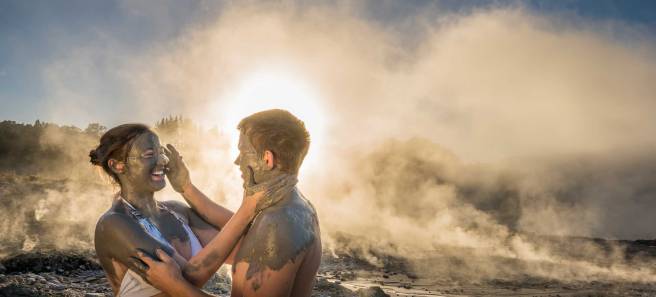
FFP_150415-6431-Edit

Tourist playing with mud. Source: Rotoruanz

Before visiting the city, however, travellers should be warned that Rotorua’s other nicknames include “Sulphur City” and “Rotten-rua”, because of the smell that results from the geothermal activity.

And speaking from personal experience, the “rotten eggs” smell is prevalent.

Interesting, but what has this got to do with the science of Parkinson’s disease?

Well, the rotten egg smell is the result of hydrogen sulfide emissions, and recently it has been suggested that this pungent gas may be having positive benefits on people, particularly with regards to Parkinson’s disease.

This idea has been proposed by Dr Yusuf Cakmak at the University of Otago in a recent commentary:

Yusuf

Title: Rotorua, hydrogen sulphide and Parkinson’s disease-A possible beneficial link?
Author: Cakmak Y.
Journal: N Z Med J. 2017 May 12;130(1455):123-125.
PMID: 28494485

In his write up, Dr Cakmak points towards two studies that have been conducted on people from Rotorua. The first focused on examining whether there was any association between asthma and chronic obstructive pulmonary disease and exposure to hydrogen sulfide in Rotorua. By examining air samples and 1,204 participants, the investigators of that study no association (the report of that study is OPEN ACCESS and can be found by clicking here).

The second study is the more interesting of the pair:
roto

Title: Chronic ambient hydrogen sulfide exposure and cognitive function.
Authors: Reed BR, Crane J, Garrett N, Woods DL, Bates MN.
Journal: Neurotoxicol Teratol. 2014 Mar-Apr;42:68-76.
PMID: 24548790                 (This article is OPEN ACCESS if you would like to read it)

In this study, the investigators recruited 1,637 adults (aged 18-65 years) from Rotorua. They conducted neuropsychological tests on the subjects, measuring visual and verbal episodic memory, attention, fine motor skills, psychomotor speed and mood. The average amount of time the participants had lived in the Rotorua region was 18 years (ranging from 3-64 years). The researchers also made measurements of hydrogen sulfide levels at the participants homes and work sites.

While the researchers found no association between hydrogen sulfide exposure and cognitive ability, they did notice something interesting in the measures of fine motor skills: individuals exposed to higher levels of hydrogen sulfide displayed faster motor response times on tasks like finger tapping. Finger tapping speed is an important part of Parkinson’s Motor Rating Scale examination tests.

The investigators behind the study concluded that the levels of hydrogen sulfide in Rotorua do not have any detrimental effect on the individuals living in the area,

Dr Cakmak, however, wondered whether “relatively high, but safe, hydrogen sulfide levels in Rotorua could help protect the degradation of dopaminergic neurons associated with Parkinson’s Disease?” (based on the better performance on the motor response time).

Hang on a second, what exactly is hydrogen sulfide?

Hydrogen sulfide (chemical symbol: H2S) is a colourless gas. Its production often results from the the breaking down of organic material in the absence of oxygen, such as in sewers (this process is called anaerobic digestion. It also occurs in volcanic and geothermal conditions.
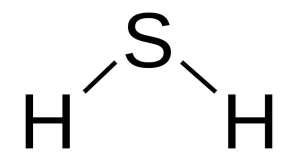
Hydrogen_sulfide

H2S. Source: Wikipedia

About 15 years ago, it was found in various organs in the body and termed a gasotransmitter. A gasotransmitter is a molecule that can be used to transmit chemical signals from one cell to another, which results in certain physiological reactions (oxygen, for example, is a gasotransmitter).

Hydrogen sulfide is now known to be cardioprotective (protection of the heart), and many years of research have demonstrated beneficial aspects of using it in therapy, such as vasodilation and lowering blood pressure, increasing levels of antioxidants, inhibiting inflammation, and activation of anti-apoptotic (anti-cell death) pathways. For a good review of hydrogen sulfide’s cardioprotective properties – click here.
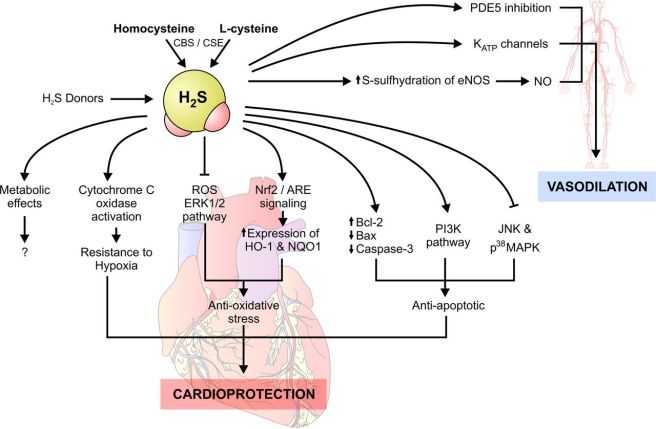
F1.large

Source: Clinsci

The demonstration of the protective properties of hydrogen sulfide in other bodily organs have led neuroscientists to start investigating whether these same benefits could be utilised in treating disorders of the brain.

And the good news is: hydrogen sulfide can have positive benefits in the brain – Click here for a good review of the brain-related research.

Has other research been conducted on hydrogen sulfide regarding Parkinson’s disease?

Yes. And here is where the story starts to get really interesting.

Initially, there were reports that hydrogen sulfide could protect cells grown in culture from exposure to various neurotoxins (Click here and here for examples).

Then hydrogen sulfide was tested in rodent models of Parkinson’s disease:

SH1

Title: Neuroprotective effects of hydrogen sulfide on Parkinson’s disease rat models.
Authors: Hu LF, Lu M, Tiong CX, Dawe GS, Hu G, Bian JS.
Journal: Aging Cell. 2010 Apr;9(2):135-46.
PMID: 20041858           (This article is OPEN ACCESS if you would like to read it)

In this study, the researchers firstly looked at what happens to hydrogen sulfide in the brains of rodent models of Parkinson’s disease. When rats were injected with a neurotoxin (6-OHDA) that kills dopamine neurons, the investigators found a significant drop in the level of hydrogen sulfide in the region where the dopamine cells reside (called the substantia nigra – an area of the brain severely affected in Parkinson’s disease).

Next the researchers gave some rodents the neurotoxin, waited three weeks and then began administering sodium hydrosulfide – which is a hydrogen sulfide donor  – every day for a further 3 weeks. They found that this treatment significantly reduced the dopamine cell loss, motor problems and inflammation in the sodium hydrosulfide treated animals. Interestingly, they saw the same neuroprotective effect when they repeated the study with a different neurotoxin (Rotenone). The investigators concluded that hydrogen sulfide “has potential therapeutic value for treatment of Parkinson’s disease”.

And this first study was followed up one year later by a study investigating inhaled hydrogen sulfide:

SH2
Title: Inhaled hydrogen sulfide prevents neurodegeneration and movement disorder in a mouse model of Parkinson’s disease.
Authors: Kida K, Yamada M, Tokuda K, Marutani E, Kakinohana M, Kaneki M, Ichinose F.
Journal: Antioxid Redox Signal. 2011 Jul 15;15(2):343-52.
PMID: 21050138            (This article is OPEN ACCESS if you would like to read it)

In this study, the investigators gave mice a neurotoxin (MPTP) and then had them breathe air with or without hydrogen sulfide (40 ppm) for 8 hours per day for one week. The mice that inhaled hydrogen sulfide displayed near normal levels of motor behaviour performance and significantly reduced levels of neurodegeneration (dopamine cell loss).

Inhalation of hydrogen sulfide also prevented the MPTP-induced activation of the brain’s helper cells (microglia and astrocytes) and increased levels of detoxification enzymes and antioxidant proteins (including heme oxygenase-1 and glutamate-cysteine ligase). Curiously, hydrogen sulfide inhalation did not significantly affect levels of reduced glutathione (we will come back to this in an upcoming post).

These first two preclinical results have been replicated many times now confirming the initial findings (Click here, here, here and here for examples). The researchers of the second ‘inhalation’ study concluded the study by suggesting that the potential therapeutic effects of hydrogen sulfide inhalation now needed to be examined in more disease relevant models of Parkinson’s disease.

And this is exactly what researchers did next:

HS5

Title: Sulfhydration mediates neuroprotective actions of parkin.
Authors: Vandiver MS, Paul BD, Xu R, Karuppagounder S, Rao F, Snowman AM, Ko HS, Lee YI, Dawson VL, Dawson TM, Sen N, Snyder SH.
Journal: Nat Commun. 2013;4:1626. doi: 10.1038/ncomms2623.
PMID: 23535647          (This article is OPEN ACCESS if you would like to read it)

The researchers conducting this study were interested in the interaction of hydrogen sulfide with the Parkinson’s disease-associated protein Parkin (also known as PARK2). They found that hydrogen sulfide actively modified parkin protein – a process called sulfhydration – and that this enhances the protein’s level of activity.

They also noted that the level of Parkin sulfhydration in the brains of patients with Parkinson’s disease is markedly reduced (a 60% reduction). These finding imply that drugs that increase levels of hydrogen sulfide in the brain may be therapeutic.

Interestingly, cells with genetic mutations in another Parkinson’s disease related gene, DJ-1, also produce less hydrogen sulfide (click here to read more about this).

Has anyone ever looked at hydrogen sulfide and alpha synuclein?

Not that we are aware of.

Alpha synuclein is the Parkinson’s disease associated protein that clusters in the Parkinsonian brain and forms Lewy bodies.

But researchers have looked at hydrogen sulfide and amyloid formation:

HS4
Title: Hydrogen sulfide inhibits amyloid formation
Authors: Rosario-Alomar MF, Quiñones-Ruiz T, Kurouski D, Sereda V, Ferreira EB, Jesús-Kim LD, Hernández-Rivera S, Zagorevski DV, López-Garriga J, Lednev IK.
Journal: J Phys Chem B. 2015 Jan 29;119(4):1265-74.
PMID: 25545790         (This article is OPEN ACCESS if you would like to read it)


Amyloid formations are large clusters of misfolded proteins that are associated with neurodegenerative conditions, like Alzheimer’s disease and Parkinson’s disease. The researchers who conducted this study were interested in the behaviour of these misfolded protein in the presence of hydrogen sulfide. What they found was rather remarkable: the addition of hydrogen sulfide completely inhibited the formation amyloid fibrils (amyloid fibril plaques are found in brains of people with Alzheimer’s disease).

jp-2014-08471v_0008

Source: NCBI

If the addition of hydrogen sulfide can reduce the level of clustered proteins in a model of Alzheimer’s disease, it would be interesting to see what it would do to alpha synuclein.

NOTE: Hydrogen sulfide levels are also reduced in the brains of people with Alzheimer’s disease (click here to read more on this topic)

Has hydrogen sulfide ever been tested in the clinic?

There are currently 17 clinical trials investigating hydrogen sulfide in various conditions (not Parkinson’s disease though).

So where can I get me some of that hydrogen sulfide?

Ok, so here is where we come in with the health warning section.

You see, hydrogen sulfide is a very dangerous gas. It is really not to be played with.

Blakely_June_Hydrogen-Sulfide

Source: Blakely

The gas is both corrosive and flammable. More importantly, at high concentrations, hydrogen sulfide gas can be fatal almost immediately (>1000 parts per milllion – source: OSHA). And the gas only exhibits the “rotten eggs” smell at low concentrations. At higher concentrations it becomes undetectable due to olfactory paralysis (luckily for the folks in Rotorua, the levels of hydrogen sulfide gas there are between 20-25 parts per billion).

Thus, we do not recommend readers to rush out and load up on hydrogen sulfide gas.

There are many foods that contain hydrogen sulfide.

For example, garlic is very rich in hydrogen sulfide. Another rich source is cooked beef, which has about 0.6mg of hydrogen sulfide per pound – cooked lamb has closer to 0.9 milligrams per pound. Heated dairy products, such as skim milk, can have approximately 3 milligrams of hydrogen sulfide per gallon, and cream has slightly more than double that amount.

Any significant change in diet by a person with Parkinson’s disease should firstly be discussed with a trained medical physician as we can not be sure what impact such a change would have on individualised treatment regimes.

What does it all mean?

Summing up: It would be interesting to look at the frequency of Parkinson’s disease in geothermal region of the world (the population of Rotorua is too small for such an analysis – 80,000 people).

Researchers believe that components of the gas emissions from these geothermal areas may be neuroprotective. Of particular interest is the gas hydrogen sulfide. At high levels, it is a very dangerous gas. At lower levels, however, researchers have shown that hydrogen sulfide has many beneficial properties, including in models of neurodegenerative conditions. These findings have led many to propose testing hydrogen sulfide in clinical trials for conditions like Parkinson’s disease.

Dr Cakmak, who we mentioned near the top of this post, goes one step further. He hypothesises that hydrogen sulfide may actually be one of the active components in the neuroprotective affect of both coffee and smoking – and with good reason. It was recently demonstrated that the certain gut bacteria, such as Prevotella, are decreased in people with Parkinson’s disease (see our post on this topic by clicking here). The consumption of coffee has been shown to help improve the Prevotella population in the gut, which may in term increase the levels of Prevotella-derived hydrogen sulfide. Similarly smokers have a decreased risk of developing Parkinson’s disease and hydrogen sulfide is a component of cigarette smoke.

All of these ideas still needs to be further tested, but we are curious to see where this research could lead. An inhaled neuroprotective treatment for Parkinson’s disease may have benefits for other neurodegenerative conditions.

Oh, and if anyone is interested, we are happy to put readers in contact with real estate agents in sunny ‘Rotten-rua’, New Zealand. The locals say that you gradually get used to the smell.


EDITOR’S NOTE: Under absolutely no circumstances should anyone reading this material consider it medical advice. The material provided here is for educational purposes only. Before considering or attempting any change in your treatment regime, PLEASE consult with your doctor or neurologist. While some of the drugs/molecules discussed on this website are clinically available, they may have serious side effects. We therefore urge caution and professional consultation before any attempt to alter a treatment regime. SoPD can not be held responsible for any actions taken based on the information provided here. 


The banner for today’s post was sourced from Trover

The Antibiotic and Parkinson’s: Oppsy, they got doxy!

maxresdefault

The general population are wrong to look up to scientists as the holders of the keys to some kind of secret knowledge that allows them to render magic on a semi-irregular basis.

All too often, the great discoveries are made by accident.

A while back, some researchers from Germany and Brazil made an interesting discovery that could have important implications for Parkinson’s disease. But they only made this discovery because their mice were feed the wrong food.

Today we’ll review their research and discuss what it could mean for Parkinson’s disease.


image-title1

Sir Alexander Fleming. Source: Biography

Sir Alexander Fleming is credited with discovering the antibiotic properties of penicillin.

But, as it is often pointed out, that the discovery was a purely chance event – an accident, if you like.

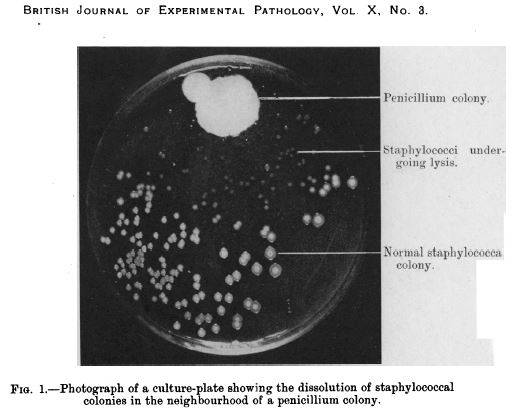
After returning from a two week holiday, Sir Fleming noticed that many of his culture dishes were contaminated with fungus, because he had not stored them properly before leaving. One mould in particular caught his attention, however, as it was growing on a culture plate with the bacteria staphylococcus. Upon closer examination, Fleming noticed that the contaminating fungus prevented the growth of staphylococci.

In an article that Fleming subsequently published in the British Journal of Experimental Pathology in 1929, he wrote, “The staphylococcus colonies became transparent and were obviously undergoing lysis … the broth in which the mould had been grown at room temperature for one to two weeks had acquired marked inhibitory, bactericidal and bacteriolytic properties to many of the more common pathogenic bacteria.”

photograph_from_1929_paper_by_fleming

Penicillin in a culture dish of staphylococci. Source: NCBI

Fleming isolated the organism responsible for prohibiting the growth of the staphylococcus, and identified it as being from the penicillium genus.

He named it penicillin and the rest is history.

Fleming himself appreciated the serendipity of the finding:

“When I woke up just after dawn on Sept. 28, 1928, I certainly didn’t plan to revolutionise all medicine by discovering the world’s first antibiotic, or bacteria killer. But I guess that was exactly what I did.” (Source)

And this gave rise to his famous quote:

“One sometimes finds what one is not looking for” (Source)

While Fleming’s discovery of the antibiotic properties of penicillin was made as he was working on a completely different research problem, the important thing to note is that the discovery was made because the evidence came to a prepared mind.

Louis-Pasteur-Quotes-1

Pasteur knew the importance of a prepared mind. Source: Thequotes

And this is the purpose of all the training in scientific research – not acquiring ‘the keys to some secret knowledge’, but preparing the investigator to notice the curious deviation.

That’s all really interesting. But what does any of this have to do with Parkinson’s disease?

Three things:

  1. Serendipity
  2. Prepared minds
  3. Antibiotics.

Huh?

Five years ago, a group of Brazilian and German Parkinson’s disease researchers made a serendipitous discovery:

While modelling Parkinson’s disease in some mice, they noticed that only two of the 40 mice that were given a neurotoxic chemical (6-OHDA) developed the motor features of Parkinson’s disease, while the rest remained healthy. This result left them scratching their heads and trying to determine what had gone wrong.

Then it clicked:

“A lab technician realised the mice had mistakenly been fed chow containing doxycycline, so we decided to investigate the hypothesis that it might have protected the neurons.” (from the press release).

The researchers had noted the ‘curious deviation’ and decided to investigate it further.

They repeated the experiment, but this time they added another group of animals which were given doxycycline in low doses (via injection) and fed on normal food (not containing the doxycycline).

And guess what: both group demonstrated neuroprotection!

Hang on a second. Two questions: 1. What exactly is 6-OHDA?
6-hydroxydopamine (or 6-OHDA) is one of several chemicals that researchers use to cause dopamine cells to die in an effort to model the cell death seen in Parkinson’s disease. It shares many structural similarities with the chemical dopamine (which is so severely affected in the Parkinson’s disease brain), and as such it is readily absorbed by dopamine cells who unwittingly assume that they are re-absorbing excess dopamine.

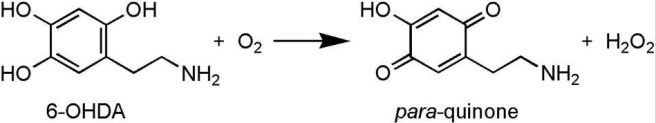
Once inside the cell, 6-OHDA rapidly transforms (via oxidisation) into hydrogen peroxide (H2O2 – the stuff folk bleach their hair with) and para-quinone (AKA 1,4-Benzoquinone). Neither of which the dopamine neurons like very much. Hydrogen peroxide in particular quickly causes massive levels of ‘oxidative stress’, resulting in the cell dying.
6OHDA

Transformation of the neurotoxin 6-OHDA. Source: NCBI

Think of 6-OHDA as a trojan horse, being absorbed by the cell because it looks like dopamine, only for the cell to work out (too late) that it’s not.

Ok, and question 2. What is doxycycline?

Doxycycline is an antibiotic that is used in the treatment of a number of types of infections caused by bacteria.

doxycycline100-1-1k_1

Remind me again, what is an antibiotic?

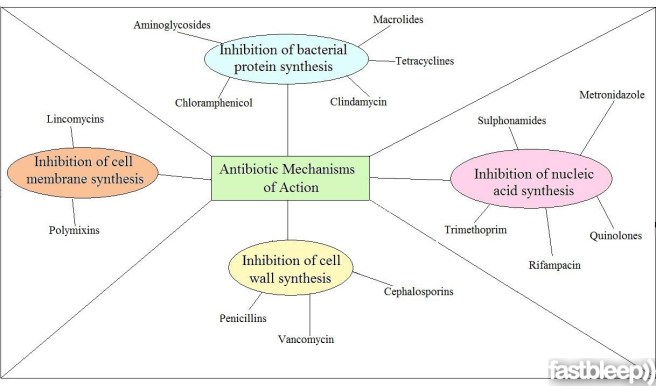
Antibiotics are a class of drugs that either kill or inhibit the growth of bacteria. They function in one of several ways, either blocking the production of bacterial proteins, inhibiting the replication of bacterial DNA (nuclei acid in the image below), or by rupturing/inhibiting the repair of the bacteria’s outer membrane/wall.

2018_1

The ways antibiotics function. Source: FastBleep

So the researchers accidentally discovered that the a bacteria-killing drug called doxycycline prevented a trojan horse called 6-OHDA from killing dopamine cells?

Basically, yeah.

And then these prepared minds followed up this serendipitous discovery with a series of experiments to investigate the phenomenon further, and they published the results recently in the journal ‘Glial’:

Glial

Title: Doxycycline restrains glia and confers neuroprotection in a 6-OHDA Parkinson model.
Authors: Lazzarini M, Martin S, Mitkovski M, Vozari RR, Stühmer W, Bel ED.
Journal: Glia. 2013 Jul;61(7):1084-100. doi: 10.1002/glia.22496. Epub 2013 Apr 17.
PMID: 23595698

In the report of their research, the investigators noted that doxycycline significantly protected the dopamine neurons and their nerve branches (called axons) in the striatum – an area of the brain where dopamine is released – when 6-OHDA was given to mice. Both oral administration and peripheral injections of doxycycline were able to have this effect.

They also reported that doxycycline inhibited the activation of astrocytes and microglial cells in the brains of the 6-OHDA treated mice. Astrocytes and microglial cells are usually the helper cells in the brain, but in the context of disease or injury these cells can quickly take on the role of judge and executioner – no longer supporting the neurons, but encouraging them to die. The researchers found that doxycycline reduced the activity of the astrocytes and microglial cells in this alternative role, allowing the dopamine cells to recuperate and survive.

The researchers concluded that the “neuroprotective effect of doxycycline may be useful in preventing or slowing the progression of Parkinson’s disease”.

Wow, was this the first time this neuroprotective effect of doxycycline has been observed?

Curiously, No.

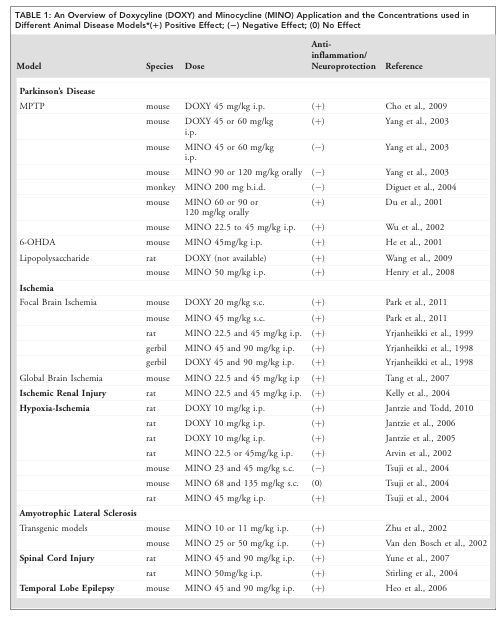
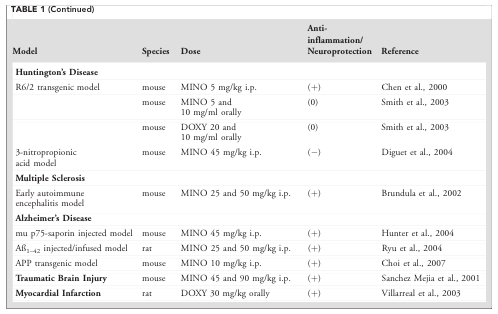
We have known of doxycycline’s neuroprotective effects in different models of brain injury since the 1990s (Click here, here and here for more on this). In fact, in their research report, the German and Brazilian researchers kindly presented a table of all the previous neuroprotective research involving doxycycline:

table1

And there was so much of it that the table carried on to a second page:

Table2

Source: Glia

And as you can see from the table, the majority of these reports found that doxycycline treatment had positive neuroprotective effects.

Is doxycycline the only antibiotic that exhibits neuroprotective properties?

No.

Doxycycline belongs to a family of antibiotics called ‘tetracyclines‘ (named for their four (“tetra-“) hydrocarbon rings (“-cycl-“) derivation (“-ine”)), and other members of this family have also been shown to display neuroprotection in models of Parkinson’s disease:

MPTP

Title: Minocycline prevents nigrostriatal dopaminergic neurodegeneration in the MPTP model ofParkinson’s disease.
Authors: Du Y, Ma Z, Lin S, Dodel RC, Gao F, Bales KR, Triarhou LC, Chernet E, Perry KW, Nelson DL, Luecke S, Phebus LA, Bymaster FP, Paul SM.
Journal: Proc Natl Acad Sci U S A. 2001 Dec 4;98(25):14669-74.
PMID: 11724929                    (This article is OPEN ACCESS if you would like to read it)

In this study, the researchers treated mice with an antibiotic called minocycline and it protected dopamine cells from the damaging effects of a toxic chemical called MPTP (or 1-methyl-4-phenyl-1,2,3,6-tetrahydropyridine). MPTP is also used in models of Parkinson’s disease, as it specifically affects the dopamine cells, while leaving other cells unaffected.

The researchers found that the neuroprotective effect of minocycline is associated a reduction in the activity of proteins that initiate cell death (for example, Caspace 1). This left the investigators concluding that ‘tetracyclines may be effective in preventing or slowing the progression of Parkinson’s disease’.

Importantly, this result was quickly followed by two other research papers with very similar results (Click here and here to read more about this). Thus, it would appear that some members of the tetracycline class of antibiotics share some neuroprotective properties.

So what did the Brazilian and German researchers do next with doxycycline?

They continued to investigate the neuroprotective effect of doxycycline in different models of Parkinson’s disease. They also got some Argentinians and Frenchies involved in the studies. And these lines of research led to their recent research report in the journal Scientific Reports:

Doxy1
Title: Repurposing doxycycline for synucleinopathies: remodelling of α-synuclein oligomers towards non-toxic parallel beta-sheet structured species.
Authors: González-Lizárraga F, Socías SB, Ávila CL, Torres-Bugeau CM, Barbosa LR, Binolfi A, Sepúlveda-Díaz JE, Del-Bel E, Fernandez CO, Papy-Garcia D, Itri R, Raisman-Vozari R, Chehín RN.
Journal: Sci Rep. 2017 Feb 3;7:41755.
PMID: 28155912                (This article is OPEN ACCESS if you would like to read it)

In this study, the researchers wanted to test doxycycline in a more disease-relevant model of Parkinson’s disease. 6-OHDA is great for screening and testing neuroprotective drugs. But given that 6-OHDA is not involved with the underlying pathology of Parkinson’s disease, it does not provide a great measure of how well a drug will do against the disease itself. So, the researchers turned their attention to our old friend, alpha synuclein – the protein which forms the clusters of protein (called Lewy bodies) in the Parkinsonian brain.

What the researchers found was fascinating: Doxycycline was able to inhibit the disease related clustering of alpha synuclein. In fact, by reshaping alpha synuclein into a less toxic version of the protein, doxycycline was able to enhance cell survival. The investigators also conducted a ‘dosing’ experiment to determine the most effect dose and they found that taking doxycycline in sub-antibiotic doses (20–40 mg/day) would be enough to exert neuroprotection. They concluded their study by suggesting that these novel effects of doxycycline could be exploited in Parkinson’s disease by “repurposing an old safe drug”.

Wow, has doxycycline ever been used in clinical trials for brain-related conditions before?

Yes.

From 2005-12,there was a clinical study to determine the safety and efficacy of doxycycline (in combination with Interferon-B-1a) in treating Multiple Sclerosis (Click here for more on this trial). The results of that study were positive and can be found here.

More importantly, the other antibiotic to demonstrate neuroprotection in models of Parkinson’s disease, minocycline (which we mentioned above), has been clinically tested in Parkinson’s disease:

title1

Title: A pilot clinical trial of creatine and minocycline in early Parkinson disease: 18-month results.
Authors: NINDS NET-PD Investigators..
Journal: Clin Neuropharmacol. 2008 May-Jun;31(3):141-50.
PMID: 18520981                (This article is OPEN ACCESS if you would like to read it)

This research report was the follow up of a 12 month clinical study that can be found by clicking here. The researchers had taken two hundred subjects with Parkinson’s disease and randomly sorted them into the three groups: creatine (an over-the-counter nutritional supplement), minocycline, and placebo (control). All of the participants were diagnosed less than 5 years before the start of the study. At 12 months, both creatine and minocycline were noted as not interfering with the beneficial effects of symptomatic therapy (such as L-dopa), but a worrying trend began with subjects dropping out of the minocycline arm of the study.

At the 18 month time point, approximately 61% creatine-treated subjects had begun to take additional treatments (such as L-dopa) for their symptoms, compared with 62% of the minocycline-treated subjects and 60% placebo-treated subjects. This result suggested that there was no beneficial effect from using either creatine or minocycline in the treatment of Parkinson’s disease, as neither exhibited any greater effect than the placebo. In addition, the investigators suggested that the decreased tolerability of minocycline was a concern.

Ok, so where do I sign up for the next doxy clinical trial?

Well, the researchers behind the Scientific reports research (discussed above) are hoping to begin planning clinical trials soon.

But theoretically speaking, there shouldn’t be a trial.

Huh?!?

There’s a good reason why not.

In fact, if you look at the comments section under the research article, a cautionary message has been left by Prof Paul M. Tulkens of the Louvain Drug Research Institute in Belgium. He points out that:

“…using antibiotics at sub-therapeutic doses is the best way to trigger the emergence of resistance (supported by many in vitro and in vivo studies). Using an antibiotic for other indications than an infection caused by a susceptible bacteria is something that should be discouraged”

And he is correct.

We recklessly over use antibiotics all over the world at the moment and they are one of the few lines of defence that we have against the bacterial world. Long term use (which Parkinson’s disease would probably require) of an antibiotic at sub-therapeutic levels will only encourage the rise of antibiotic resistant bacteria (possibly within individuals).

The resistance of bacteria to antibiotics can occur spontaneously via several means (for example, through random genetic mutations during cell division). With the right mutation (inferring antibiotic resistance), an individual bacteria would then have a natural advantage over their friends and it would survive our attempts to kill it with antibiotics. Being resistant to antibiotic would leave that bacteria to wreak havoc upon us.
Its the purest form of natural selection.

natural-selection_140211

How bacteria become resistant to antibiotics. Source: Reactgroup

And antibiotic resistant bacteria are fast becoming a major health issue for us, with the number of species of bacteria developing resistance increasing every year (Click here for a good review on factors contributing to the emergence of resistance, and click here for a review of the antibiotic resistant bacteria ‘crisis’).

But don’t be upset on the Parkinson’s disease side of things. Prof Tulken adds that:

“If doxycycline really acts as the authors propose, the molecular targets are probably very different from those causing antibacterial activity. it should therefore be possible to dissociate these effect from the antibacterial effects and to get active compounds devoid of antibacterial activity This is where research must go to rather than in trying to use doxycycline itself.”

And he is correct again.

Rather than tempting disaster, we need to take the more prudent approach.

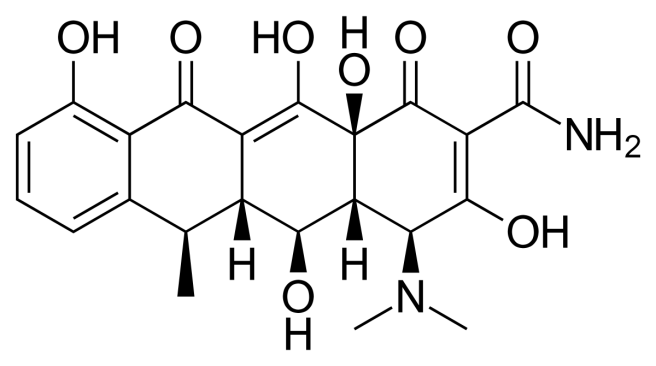
Independent researchers must now attempt to replicate the neuroprotective results in carefully controlled conditions. At the same time, chemists should conduct an analysis of the structure of doxycycline to determine which parts of it are having this neuroprotective effect.

Doxycycline_structure.svg

The structure of doxycycline. Source: Wikipedia

If researchers can isolate those neuroprotective elements and those same parts are separate from the antibiotic properties, then we may well have another experimental drug for treating Parkinson’s disease.

And the good news is that researchers are already reasonably sure that the mechanisms of the neuroprotective effect of doxycycline are distinct from its antimicrobial action.

So what does it all mean?

Researchers have once again identified an old drug that can perform a new trick.

The bacteria killing antibiotic, doxycycline, has a long history of providing neuroprotection in models of brain disease, but recently researchers have demonstrated that doxycycline may have beneficial effects on particular aspects of Parkinson’s disease.

Given that doxycycline is an antibiotic, we must be cautious in our use of it. It will be interesting to determine which components of doxycycline are neuroprotective, and whether other antibiotics share these components. Given the number of researchers now working in this area, it should not take too long.

We’ll let you know when we hear something.


EDITOR’S NOTE: Under absolutely no circumstances should anyone reading this material consider it medical advice. The material provided here is for educational purposes only. Before considering or attempting any change in your treatment regime, PLEASE consult with your doctor or neurologist. While some of the drugs discussed on this website are clinically available, they may have serious side effects. We therefore urge caution and professional consultation before any attempt to alter a treatment regime. SoPD can not be held responsible for any actions taken based on the information provided here. 


The banner for today’s post was sourced from Youtube

Iron, life force, and Parkinson’s disease

pranaLogo

‘Prana’ is a Hindu Sanskrit word meaning “life force”.

An Australian biotech company has chosen this word for their name.

Recently Prana Biotechnology Ltd announced some exciting results from their Parkinson’s disease research programme.

In today’s post we will look at what the company is doing, the science underlying the business plan, and review the results they have so far.


adpd2017

Source: ADPD2017

At the end of March, over 3000 researchers in the field of neurodegeneration gathered in the Austrian capital of Vienna for the 13th International Conference on Alzheimer’s and Parkinson’s Diseases and Related Neurological Disorders (also known as ADPD2017).

crop

The Vienna city hall. Source: EUtourists

A lot of interesting new research in the field of Parkinson’s disease was presented at the conference (we will look at some other presentation in future posts), but one was of particular interest to us here at SoPD HQ.

The poster entitled: ‘Abstract: 104 – PBT434 prevents neuronal loss, motor function and cognitive impairment in preclinical models of movement disorders by modulation of intracellular iron’, was presented by Associate Professor David Finkelstein, of the Florey Institute of Neuroscience and Mental Health (Melbourne, Australia).

Unfortunately the ADPD2017 conference’s scientific programme search engine does not allow for individual abstracts to be linked to on the web so if you would like to read the abstract, you will need to click here for the search engine page and search for ‘PBT434’ or ‘Finkelstein’ in the appropriate boxes.

Prof Finkelstein was presenting preclinical research that had been conducted by an Australian biotech company called Prana Biotechnology Ltd.

promo1

Source: Prana Biotechnology Ltd

What does the company do?

Prana Biotechnology Ltd has a large portfolio of over 1000 small chemical agents that they have termed ‘MPACs’ (or Metal Protein Attenuating Compounds). These compounds are designed to interrupt the interactions between particular metals and target proteins in the brain. The goal of this interruption is to prevent deterioration of brain cells in neurodegenerative conditions.

For Parkinson’s disease, the company is proposing a particular iron chelator they have called PBT434.

What is an iron chelator?

Iron chelator therapy involves the removal of excess iron from the body with special drugs. Chelate is from the Greek word ‘chela’ meaning “claw”.

chelationtherapy_edited-01

Chelator therapy. Source: Stanford

Iron overload in the body is a common medical problem, sometimes arising from disorders of increased iron absorption such as hereditary haemochromatosis. Iron chelator therapy represents one method of reducing the levels of iron in the body.

But why is iron overload a problem?

iron

Iron. Source: GlobalSpec

Good question. It involves the basic properties of iron.

Iron is a chemical element (symbol Fe). It has the atomic number 26 and by mass it is the most common element on Earth (it makes up much of Earth’s outer and inner core). It is absolutely essential for cellular life on this planet as it is involved with the interactions between proteins and enzymes, critical in the transport of oxygen, and required for the regulation of cell growth and differentiation.

So why then – as Rosalind asked in Shakespeare’s As You Like It – “can one desire too much of a good thing?”

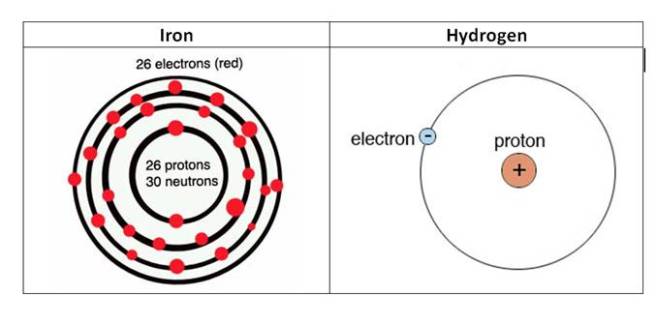
Well, if you think back to high school chemistry class you may recall that there are these things called electrons. And if you have a really good memory, you will recall that the chemical hydrogen has one electron, while iron has 26 (hence the atomic number 26).

atoms

The electrons of iron and hydrogen. Source: Hypertonicblog

Iron has a really interesting property: it has the ability to either donate or take electrons. And this ability to mediate electron transfer is one of the reasons why iron is so important in the body.

Iron’s ability to donate and accept electrons means that when there is a lot of iron present it can inadvertently cause the production of free radicals. We have previously discussed free radicals (Click here for that post), but basically a free radical is an unstable molecule – unstable because they are missing electrons.

imgres

How free radicals and antioxidants work. Source: h2miraclewater

In an unstable format, free radicals bounce all over the place, reacting quickly with other molecules, trying to capture the much needed electron to re-gain stability. Free radicals will literally attack the nearest stable molecule, to steal an electron. This leads to the “attacked” molecule becoming a free radical itself, and thus a chain reaction is started. Inside a living cell this can cause terrible damage, ultimately killing the cell.

Antioxidants can help try and restore the balance, but in the case of iron overload iron doctors will prescribe chelator treatment to deal with the situation more efficiently. By soaking up excess iron, we can limit the amount of damage caused by the surplus of iron.

So what research has been done regarding iron content and the Parkinsonian brain?

Actually, quite a lot.

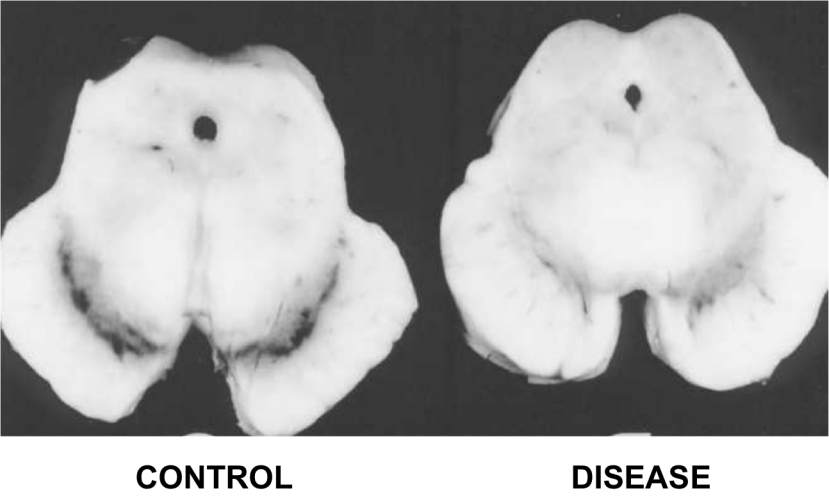
In 1968, Dr Kenneth Earle used an X-ray based technique to examine the amount of iron in the substantia nigra of people with Parkinson’s disease (Source). The substantial nigra is one of the regions in the brain most badly damaged by the condition – it is where most of the brain’s dopamine neurones resided.

d1ea3d21c36935b85043b3b53f2edb1f87ab7fa6

The dark pigmented dopamine neurons in the substantia nigra are reduced in the Parkinson’s disease brain (right). Source:Memorangapp

Earle examined 11 samples and compared them to unknown number of control samples and his results were a little startling:

The concentration of iron in Parkinsonian samples was two times higher than that of the control samples.

Since that first study, approximately 30 investigations have been made into levels of iron in the Parkinsonian brain. Eleven of those studies have replicated the Earle study by looking at postmortem tissue. They have used different techniques and the results have varied somewhat:

  • Sofic et al. (1988)                             1.8x increase in iron levels
  • Dexter et al. (1989)                         1.3x increase in iron levels
  • Uitti et al. (1989)                              1.1x increase in iron levels
  • Riederer et al 1989                         1.3x increase in iron levels
  • Griffiths and Crossman (1993)     2.0x increase in iron levels
  • Mann et al. (1994)                           1.6x increase in iron levels
  • Loeffler et al. (1995)                       0.9   (lower)
  • Galazka-Friedman et al., 1996     1.0   (no difference)
  • Wypijewska et al. (2010)               1.0   (no difference)
  • Visanji et al, 2013                            1.7x increase in iron levels

Overall, however, there does appear to be a trend in the direction of higher levels of iron in the Parkinsonian brains. A recent meta-analysis of all this data confirmed this assessment as well as noting an increase in the caudate putamen (the region of the brain where the dopamine neuron branches release their dopamine – Click here for that study).

Brain imaging of iron (using transcranial sonography and magnetic resonance imaging (MRI)) has also demonstrated a strong correlation between iron levels in the substantia nigra region and Parkinson’s disease severity/duration (Click here and here to read more on this).

Thus, there appears to be an increase of iron in the regions most affected by Parkinson’s disease and this finding has lead researchers to ask whether reducing this increase in iron may help in the treatment of Parkinson’s disease.

How could iron overload be bad in Parkinson’s disease?

Well in addition to causing the production of free radicals, there are many possible ways in which iron accumulation could be aggravating cell loss in Parkinson’s disease.

983245.fig.001

Possible causes and consequences of iron overload in Parkinson’s disease. Source: Hindawi

High levels of iron can cause the oxidation of dopamine, which results in the production of hydrogen peroxide (H2O2 – a reactive oxygen species – the stuff that is used to bleach hair and is also used as a propellant in rocketry!). This reaction can cause further oxidative stress that can then lead to a range of consequences including protein misfolding, lipid peroxidation (which can cause the accumulation of the Parkinson’s associated protein alpha synuclein), mitochondrial dysfunction, and activation of immune cells in the brain.

And this is just a taster of the consequences.

For further reading on this topic we recommend two very good reviews – click here and here.

Ok, so iron overload is bad, but what was the research presented in Austria?

The abstract:

Title: PBT434 prevents neuronal loss, motor function and cognitive impairment in preclinical models of movement disorders by modulation of intracellular iron
Authors: D. Finkelstein, P. Adlard, E. Gautier, J. Parsons, P. Huggins, K. Barnham, R. Cherny
Location: C01.a Posters – Theme C – Alpha-Synucleinopathies

The researchers at Prana Biotechnology Ltd assessed the potential of one of their candidate drugs, PBT434, in both cell culture and animal models of Parkinson’s disease. The PBT434 drug was selected for further investigation based on its performance in cell culture assays designed to test the inhibition of oxidative stress and iron-mediated aggregation of Parkinson’s associated proteins like alpha synuclein.

PBT434 significantly reduced the accumulation of alpha synuclein and markers of oxidative stress, and prevented neuronal loss.

The investigators also demonstrated that orally administered PBT434 readily crossed the blood brain barrier and entered the brain. In addition the drug was well-tolerated in the experimental animals and improved motor function in toxin-induced (MPTP and 6-hydroxydopamine) and transgenic mouse models of Parkinson’s disease (alpha synuclein -A53T and tau – rTg4510).

These results are in agreement with previous studies that have looked at iron chelator therapy in models of Parkinson’s disease (Click here, here and here for some examples)

Interestingly, PBT434 also demonstrated neuroprotective properties in animal models of multiple systems atrophy (or MSA). Suggesting that perhaps iron chelation could be a broad neuroprotective approach.

The researchers concluded that this preclinical data demonstrates the efficacy of PBT434 as a clinical candidate for Parkinson’s disease. PBT434 shows a strong toxicology profile and favourable therapeutic activity.  Prana is preparing its pre-clinical development package for PBT434 to initiate human clinical trials.

Does Prana have any other drugs in clinical trials?

Yes, they do.

pipeline-assets07-1024x571

Source: Prana

Prana Biotechnology has another product called PBT2.

The company currently has two clinical trial programs for PBT2 focused on two other neurodegenerative diseases: Alzheimer’s disease and Huntington’s disease.

The Alzheimer’s study was called the IMAGINE Trial, but (there is always a ‘but’) recently PBT2 failed to meet its primary endpoint (significantly reducing levels of beta-amyloid  – the perceived bad guy in Alzheimer’s disease) in a phase III trial of mild Alzheimer’s disease. PBT2 was, however, shown to be safe and very well tolerated over the 52 week trial, with no difference in the occurrence of adverse events between the placebo and treated groups.

In addition, there was less atrophy (shrinkage) in the brains of those patients treated with PBT2 when compared to control brains, 2.6% and 4.0%, respectively (based on brain imaging).  The company is tracking measures of brain volume and cognition in a 12 month extension study. It could be interesting to continue that follow up long term to evaluate the consequences of long term use of this drug on Alzheimer’s disease – even if the effect is minimal, any drug that can slow the disease down is useful and could be used in conjunction with other neuroprotective medications.

For Huntington’s disease, the company is also using the PBT2 drug and this study has had a bit more success. The study, called Reach2HD, was a six month phase II clinical trial in 109 patients with early to mid-stage Huntington’s disease, across 20 sites in the US and Australia. The company was aiming to assess the safety profile of this drug in this particular condition, as well as determining the motor and behavioural benefits.

In the ReachHD study, PBT2 showed signs of improving some aspects of cognitive function in the study, which potentially represents a major event for a disease for which there is very little in the way of medical treatments.

For a full description of the PBT2 trials, see this wikipedia page on the topic.

Is Prana the only research group working on iron chelators technology for Parkinson’s disease?

No.

There is a large EU-based consortium called FAIR PARK II, which is running a five year trial (2015 – 2020) of the iron chelator deferiprone (also known as Ferriprox). The study is a multi-centre, placebo-controlled, randomised clinical trial involving 338 people with recently diagnosed Parkinson’s disease.

LOGO_FAIR_PARK_TIME1

The population will be divided into two group (169 subjects each). They will then be assigned either deferiprone (15 mg/kg twice a day) or a placebo. Each subject will be given 9-months of treatment followed by a 1-month post-treatment monitoring period, in order to assess the disease-modifying effect of deferiprone (versus placebo).

Product-14303066240

Deferiprone. Source: SGPharma

As far as we are aware, this FAIR PARK II clinical trial is still recruiting participants – please click here to read more about this – thus it will most likely be some time before we hear the results of this study.

Are there natural sources of chelators?

Yes there are. In fact, many natural antioxidants exert some chelating activities.

Prominent among the natural sources of chelators: Green tea has components of plant extracts, such as epigallocatechin gallate (EGCG – which we have previously discussed in regards to Parkinson’s disease, click here to read that post) which possess structures which infer metal chelating properties.

As we have said before people, drink more green tea!

cup and teapot of linden tea and flowers isolated on white

Anyone fancy a cuppa? Source: Expertrain

So what does it all mean?

Summing up: We do not know what causes Parkinson’s disease. Most of our experimental treatments are focused on the biological events that occur in the brain around and after the time of diagnosis. These include an apparent accumulation of iron in affected brain regions.

Research groups are currently experimenting with drugs that reduce the levels of iron in the brain as a potential treatment for Parkinson’s disease. Preclinical data certainly look positive. We will now have to wait and see if those results translate into the human.

Previous clinical trials of metal chelators in neurodegeneration have had mixed success in demonstrating positive benefits. It may well be, however, that this treatment approach should be used in conjunction with other neuroprotective approaches – as a supplement. It will be interesting to see how Prana Biotechnology’s drug PBT434 fares in human clinical trials for Parkinson’s disease.

Stay tuned for more on this.


UPDATE – 3rd May 2017

Today the results of a double-blind, phase II clinical trial of iron chelator deferiprone in Parkinson’s disease were published. The results of the study indicate a mildly positive effect (though not statistically significant) after 6 months of daily treatment.

Iron1
Title: Brain iron chelation by deferiprone in a phase 2 randomised double-blinded placebo controlled clinical trial in Parkinson’s disease
Authors: Martin-Bastida A, Ward RJ, Newbould R, Piccini P, Sharp D, Kabba C, Patel MC, Spino M, Connelly J, Tricta F, Crichton RR & Dexter DT
Journal: Scientific Reports (2017), 7, 1398.
PMID: 28469157        (This article is OPEN ACCESS if you would like to read it)

In this Phase 2 randomised, double-blinded, placebo controlled clinical trial, the researchers recruited 22 people with early stage Parkinson’s disease (disease duration of less than 5 years; 12 males and 10 females; aged 50–75 years). They were randomly assigned to either a placebo group (8 participants), or one of two deferiprone treated groups: 20 mg/kg per day (7 participants) or 30 mg/kg per day (7 participants). The treatment was two daily oral doses (taken morning and evening), and administered for 6 months with neurological examinations, brain imaging and blood sample collections being conducted at 0, 3 and 6 months.

Deferiprone therapy was well tolerated and brain imaging indicated clearance of iron from various parts of the brain in the treatment group compared to the placebo group. Interestingly, the 30 mg/kg deferiprone treated group demonstrated a trend for improvement in motor-UPDRS scores and quality of life (although this was not statistically significance). The researchers concluded that “more extensive clinical trials into the potential benefits of iron chelation in PD”.

Given the size of the groups (7 people) and the length of the treatment period (only 6 months) in this study it is not really a surprise that the researchers did not see a major effect. That said, it is very intriguing that they did see a trend towards motor score benefits in the  30 mg/kg deferiprone group – remembering that this is a double blind study (so even the investigators were blind as to which group the subjects were in).

We will now wait to see what the FAIR PARK II clinical trial finds.


UPDATE: 28th June 2017

Today, the research that Prana biotechnology Ltd was presenting in Vienna earlier this year was published:

Prana

Title: The novel compound PBT434 prevents iron mediated neurodegeneration and alpha-synuclein toxicity in multiple models of Parkinson’s disease.
Authors: Finkelstein DI, Billings JL, Adlard PA, Ayton S, Sedjahtera A, Masters CL, Wilkins S, Shackleford DM, Charman SA, Bal W, Zawisza IA, Kurowska E, Gundlach AL, Ma S, Bush AI, Hare DJ, Doble PA, Crawford S, Gautier EC, Parsons J, Huggins P, Barnham KJ, Cherny RA.
Journal: Acta Neuropathol Commun. 2017 Jun 28;5(1):53.
PMID: 28659169             (This article is OPEN ACCESS if you would like to read it)

The results suggest that PBT434 is far less potent than deferiprone or deferoxamine at lowering cellular iron levels, but this weakness is compensated by the reduced levels of alpha synuclein accumulation in models of Parkinson’s disease. PBT434 certainly appears to be neuroprotective demonstrating improvements in motor function, neuropathology and biochemical markers of disease state in three different animal models of Parkinson’s disease.

The researchers provide little information as to when the company will be exploring clinical trials for this drug, but in the press release associated with the publication, Dr David Stamler (Prana’s Chief Medical Officer and Senior Vice President, Clinical Development) was quoted saying that they “are eager to begin clinical testing of PBT434”. We’ll keep an eye to the ground for any further news.


FULL DISCLOSURE: Prana Biotechnology Ltd is an Australasian biotechnology company that is publicly listed on the ASX. The information presented here is for educational purposes. Under no circumstances should investment decisions be made based on the information provided here. The SoPD website has no financial or beneficial connection to either company. We have not been approached/contacted by the company to produce this post, nor have we alerted them to its production. We are simply presenting this information here as we thought the science of what the company is doing might be of interest to other readers. 

In addition, under absolutely no circumstances should anyone reading this material consider it medical advice. The material provided here is for educational purposes only. Before considering or attempting any change in your treatment regime, PLEASE consult with your doctor or neurologist. Metal chelators are clinically available medications, but it is not without side effects (for more on this, see this website). We urge caution and professional consultation before altering a treatment regime. SoPD can not be held responsible for any actions taken based on the information provided here. 


The banner for today’s post was sourced from Prana

On astrocytes and neurons – reprogramming for Parkinson’s

NG2+-flare

Last week scientists in Sweden published research demonstrating a method by which the supportive cells of the brain (called astrocytes) can be re-programmed into dopamine neurons… in the brain of a live animal!

It was a really impressive trick and it could have major implications for Parkinson’s disease.

In today’s post is a long read, but in it we will review the research leading up to the study, explain the science behind the impressive feat, and discuss where things go from here.


human-body-cells-25962548

Different types of cells in the body. Source: Dreamstime

In your body at this present moment in time, there is approximately 40 trillion cells (Source).

The vast majority of those cells have developed into mature types of cell and they are undertaking very specific functions. Muscle cells, heart cells, brain cells – all working together in order to keep you vertical and ticking.

Now, once upon a time we believed that the maturation (or the more technical term: differentiation) of a cell was a one-way street. That is to say, once a cell became what it was destined to become, there was no going back. This was biological dogma.

Then a guy in Japan did something rather amazing.

Who is he and what did he do?

This is Prof Shinya Yamanaka:

yamanaka-s

Prof Shinya Yamanaka. Source: Glastone Institute

He’s a rockstar in the scientific research community.

Prof Yamanaka is the director of Center for induced Pluripotent Stem Cell Research and Application (CiRA); and a professor at the Institute for Frontier Medical Sciences at Kyoto University.

But more importantly, in 2006 he published a research report demonstrating how someone could take a skin cell and re-program it so that was now a stem cell – capable of becoming any kind of cell in the body.

Here’s the study:

IPS2

Title: Induction of pluripotent stem cells from mouse embryonic and adult fibroblast cultures by defined factors.
Authors: Takahashi K, Yamanaka S.
Journal: Cell. 2006 Aug 25;126(4):663-76.
PMID: 16904174                (This article is OPEN ACCESS if you would like to read it)

Shinya Yamanaka‘s team started with the hypothesis that genes which are important to the maintenance of embryonic stem cells (the cells that give rise to all cells in the body) might also be able to cause an embryonic state in mature adult cells. They selected twenty-four genes that had been previously identified as important in embryonic stem cells to test this idea. They used re-engineered retroviruses to deliver these genes to mouse skin cells. The retroviruses were emptied of all their disease causing properties, and could thus function as very efficient biological delivery systems.

The skin cells were engineered so that only cells in which reactivation of the embryonic stem cells-associated gene, Fbx15, would survive the testing process. If Fbx15 was not turned on in the cells, they would die. When the researchers infected the cells with all twenty-four embryonic stem cells genes, remarkably some of the cells survived and began to divide like stem cells.

In order to identify the genes necessary for the reprogramming, the researchers began removing one gene at a time from the pool of twenty-four. Through this process, they were able to narrow down the most effective genes to just four: Oct4, Sox2, cMyc, and Klf4, which became known as the Yamanaka factors.

This new type of cell is called an induced pluripotent stem (IPS) cell – ‘pluripotent’ meaning capable of any fate.

The discovery of IPS cells turned biological dogma on it’s head.

And in acknowledgement of this amazing bit of research, in 2012 Prof Yamanaka and Prof John Gurdon (University of Cambridge) were awarded the Nobel prize for Physiology and Medicine for the discovery that mature cells can be converted back to stem cells.

hero-10312012_0.jpg

Prof Yamanaka and Prof Gurdon. Source: UCSF

Prof Gurdon achieved the feat in 1962 when he removed the nucleus of a fertilised frog egg cell and replaced it with the nucleus of a cell taken from a tadpole’s intestine. The modified egg cell then grew into an adult frog! This fascinating research proved that the mature cell still contained the genetic information needed to form all types of cells.

EDITOR’S NOTE: We do not want to be accused of taking anything away from Prof Gurdon’s contribution to this field (which was great!) by not mentioning his efforts here. For the sake of saving time and space, we are focusing on Prof Yamanaka’s research as it is more directly related to today’s post.


ips-cells

Making IPS cells. Source: learn.genetics

This amazing discovery has opened new doors for biological research and provided us with incredible opportunities for therapeutic treatments. For example, we can now take skins cells from a person with Parkinson’s disease and turn those cells into dopamine neurons which can then be tested with various drugs to see which treatment is most effective for that particular person (personalised medicine in it’s purest form).

nature10761-f2.2

Some of the option available to Parkinson’s disease. Source: Nature

Imagination is literally the only limiting factor with regards to the possible uses of IPS cell technology.

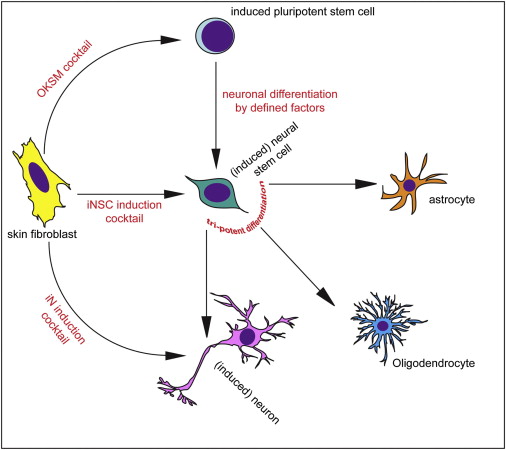
Shortly after Yamanaka’s research was published in 2006, however, the question was asked ‘rather than going back to a primitive state, can we simply change the fate of a mature cell directly?’ For example, turn a skin cell into a neuron.

This question was raised mainly to address the issue of ‘age’ in the modelling disease using IPS cells. Researchers questioned whether an aged mature cell reprogrammed into an immature IPS cell still carried the characteristics of an aged cell (and can be used to model diseases of the aged), or would we have to wait for the new cell to age before we can run experiments on it. Skin biopsies taken from aged people with neurodegenerative conditions may lose the ‘age’ element of the cell and thus an important part of the personalised medicine concept would be lost.

So researchers began trying to ‘re-program’ mature cells. Taking a skin cell and turning it directly into a heart cell or a brain cell.

And this is probably the craziest part of this whole post because they actually did it! 

figure 1

Different methods of inducing skin cells to become something else. Source: Neuron

In 2010, scientists from Stanford University published this report:

Nature2

Title: Direct conversion of fibroblasts to functional neurons by defined factors
Authors: Vierbuchen T, Ostermeier A, Pang ZP, Kokubu Y, Südhof TC, Wernig M.
Journal: Nature. 2010 Feb 25;463(7284):1035-41.
PMID: 20107439

In this study, the researchers demonstrated that the activation of three genes (Ascl1, Brn2 and Myt1l) was sufficient to rapidly and efficiently convert skin cells into functional neurons in cell culture. They called them ‘iN’ cells’ or induced neuron cells. The ‘re-programmed’ skin cells made neurons that produced many neuron-specific proteins, generated action potentials (the electrical signal that transmits a signal across a neuron), and formed functional connection (or synapses) with neighbouring cells. It was a pretty impressive achievement, which they beat one year later by converting mature liver cells into neurons – Click here to read more on this – Wow!

The next step – with regards to our Parkinson’s-related interests – was to convert skin cells directly into dopamine neurons (the cells most severely affected in the condition).

And guess what:

PSNA

Title: Direct conversion of human fibroblasts to dopaminergic neurons.
Authors: Pfisterer U, Kirkeby A, Torper O, Wood J, Nelander J, Dufour A, Björklund A, Lindvall O, Jakobsson J, Parmar M
Journal:  Proc Natl Acad Sci U S A (2011) 108:10343-10348.
PMID: 21646515          (This article is OPEN ACCESS if you would like to read it)

In this study, Swedish researchers confirmed that activation of Ascl1, Brn2, and Myt1l re-programmed human skin cells directly into functional neurons. But then if they added the activation of two additional genes, Lmx1a andFoxA2 (which are both involved in dopamine neuron generation), they could convert skin cells directly into dopamine neurons. And those dopamine neurons displayed all of the correct features of normal dopamine neurons.

With the publication of this research, it suddenly seemed like anything was possible and people began make all kinds of cell types out of skin cells. For a good review on making neurons out of skin cells – Click here.

Given that all of this was possible in a cell culture dish, some researchers started wondering if direct reprogramming was possible in the body. So they tried.

And again, guess what:

Nature1

Title: In vivo reprogramming of adult pancreatic exocrine cells to beta-cells.
Authors: Zhou Q, Brown J, Kanarek A, Rajagopal J, Melton DA.
Journal: Nature. 2008 Oct 2;455(7213):627-32.
PMID: 18754011

Using the activation of three genes (Ngn3, Pdx1 and Mafa), the investigators behind this study re-programmed differentiated pancreatic exocrine cells in adult mice into cells that closely resemble b-cells. And all of this occurred inside the animals, while the animals were wandering around & doing their thing!

Now naturally, researchers in the Parkinson’s disease community began wondering if this could also be achieved in the brain, with dopamine neurons being produced from re-programmed cells.

And (yet again) guess what:

in-vivo

Title: Generation of induced neurons via direct conversion in vivo
Authors: Torper O, Pfisterer U, Wolf DA, Pereira M, Lau S, Jakobsson J, Björklund A, Grealish S, Parmar M.
Journal: Proc Natl Acad Sci U S A. 2013 Apr 23;110(17):7038-43.
PMID: 23530235         (This article is OPEN ACCESS if you would like to read it)

In this study, the Swedish scientists (behind the previous direct re-programming of skin cells into dopamine neurons) wanted to determine if they could re-program cells inside the brain. Firstly, they engineered skin cells with the three genes (Ascl1, Brn2a, & Myt1l) under the control of a special chemical – only in the presence of the chemical, the genes would be activated. They next transplanted these skin cells into the brains of mice and began adding the chemical to the drinking water of the mice. At 1 & 3 months after transplantation, the investigators found re-programmed cells inside the brains of the mice.

Next, the researchers improved on their recipe for producing dopamine neurons by adding the activation of two further genes: Otx2 and Lmx1b (also important in the development of dopamine neurons). So they were now activating a lot of genes: Ascl1, Brn2a, Myt1l, Lmx1a, FoxA2, Otx2 and Lmx1b. Unfortunately, when these reprogrammed cells were transplanted into the brain, few of them survived to become mature dopamine neurons.

The investigators then ask themselves ‘do we really need to transplant cells? Can’t we just reprogram cells inside the brain?’ And this is exactly what they did! They injected the viruses that allow for reprogramming directly into the brains of mice. The experiment was designed so that the cargo of the viruses would only become active in the astrocyte cells, not neurons. And when the researchers looked in the brains of these mice 6 weeks later, they found numerous re-programmed neurons, indicating that direct reprogramming is possible in the intact brain.

So what was so special about the research published last week about? Why the media hype?

The research published last week, by another Swedish group, took this whole process one step further: Not only did they re-program astrocytes in the brain to become dopamine neurons, but they also did this on a large enough scale to correct the motor issues in a mouse model of Parkinson’s disease.

Here is the study:
Arenas

Title: Induction of functional dopamine neurons from human astrocytes in vitro and mouse astrocytes in a Parkinson’s disease model
Authors: di Val Cervo PR, Romanov RA, Spigolon G, Masini D, Martín-Montañez E, Toledo EM, La Manno G, Feyder M, Pifl C, Ng YH, Sánchez SP, Linnarsson S, Wernig M, Harkany T, Fisone G, Arenas E.
Journal: Nature Biotechnology (2017) doi:10.1038/nbt.3835
PMID: 28398344

These researchers began this project 6 years ago with a new cocktail of genes for reprogramming cells to become dopamine neurons. They used the activation of NEUROD1, ASCL1 and LMX1A, and a microRNA miR218 (microRNAs are genes that produce RNA, but not protein – click here for more on this). These genes improved the reprogramming efficiency of human astrocytes to 16% (that is the percentage of astrocytes that were infected with the viruses and went on to became dopamine neurons). The researchers then added some chemicals to the reprogramming process that helps dopamine neurons to develop in normal conditions, and they observed an increase in the level of reprogramming to approx. 30%. And these reprogrammed cells display many of the correct properties of dopamine neurons.

Next the investigators decided to try this conversion inside the brains of mice that had Parkinson’s disease modelled in them (using a neurotoxin). The delivery of the viruses into the brains of these mice resulted in reprogrammed dopamine neurons beginning to appear, and 13 weeks after the viruses were delivered, the researchers observed improvements in the Parkinson’s disease related motor symptoms of the mice. The scientists concluded that with further optimisation, this reprogramming approach may enable clinical therapies for Parkinson’s disease, by the delivery of genes rather than transplanted cells.

How does this reprogramming work?

As we have indicated above, the re-programming utilises re-engineered viruses. They have been emptied of their disease causing elements, allowing us to use them as very efficient biological delivery systems. Importantly, retroviruses infect dividing cells and integrate their ‘cargo’ into the host cell’s DNA.

RetroviralIntegration

Retroviral infection and intergration into DNA. Source: Evolution-Biology

The ‘cargo’ in the case of IPS cells, is a copy of the genes that allow reprogramming (such as the Yamanaka genes), which the cell will then start to activate, resulting in the production of protein for those genes. These proteins subsequently go on to activate a variety of genes required for the maintenance of embryonic stem cells (and re-programming of mature cells).

And viruses were also used for the re-programming work in the brain as well.

There is the possibility that one day we will be able to do this without viruses – in 2013, researchers made IPS cells using a specific combination of chemicals (Click here to read more about this) – but at the moment, viruses are the most efficient biological targeting tool we have.

So what does it all mean?

Last week researchers is Sweden published research explaining how they reprogrammed some of the helper cells in the brains of Parkinsonian mice so that they turned into dopamine neurons and helped to alleviate the symptoms the mice were feeling.

This result and the trail of additional results outlined above may one day be looked back upon as the starting point for a whole new way of treating disease and injury to particular organs in the body. Suddenly we have the possibility of re-programming cells in our body to under take a new functions to help combat many of the conditions we suffer.

It is important to appreciate, however, that the application of this technology is still a long way from entering the clinic (a great deal of optimisation is required). But the fact that it is possible and that we can do it, raises hope of more powerful medical therapies for future generations.

As the researchers themselves admit, this technology is still a long way from the clinic. Improving the efficiency of the technique (both the infection of the cells and the reprogramming) will be required as we move down this new road. In addition, we will need to evaluate the long-term consequences of removing support cells (astrocytes) from the carefully balanced system that is the brain. Future innovations, however, may allow us to re-program stronger, more disease-resistant dopamine neurons which could correct the motor symptoms of Parkinson’s disease without being affected by the disease itself (as may be the case in transplanted cells – click here to read more about this).

Watch for a lot more research coming from this topic.


The banner for today’s post was sourced from Greg Dunn (we love his work!)

Stimulating research in London (Canada)

Spinal-Cord-final

Recently the SoPD has been contacted by readers asking about this video:

http://london.ctvnews.ca/video?clipId=1080895

The video presents a news article from Canada describing a clinical study of spinal cord stimulation for Parkinson’s disease.

In today’s post we review what spinal cord stimulation is and what research has been done in Parkinson’s disease.


should-say-50th-birthday-speech_67e6879f1e6fbd7

50 years celebration. Source: Reference

As many readers will be aware from 2017 represents the 200 year anniversary of the first description of Parkinson’s disease by one Mr James Parkinson.

Many readers will not be aware, however, that 2017 is also represents the 50th anniversary of the first use of a technique called spinal cord stimulation:

What is spinal cord stimulation?

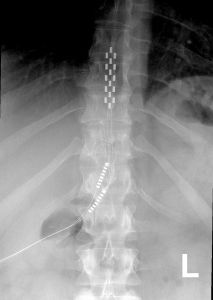
Anterior_thoracic_SCS

An x-ray of the spine with a stimulator implanted (towards the top of the image, and cords leading off to the bottom left). Source: Wikipedia

A spinal cord stimulator involves a small device being used to apply pulsed electrical signals to the spinal cord. It is generally used for pain relief, but it has recently been tested in a variety of other medical conditions.

The device is a column of stimulating electrodes that is surgically implanted in the epidural space of the spine. And before you ask: the epidural space is the area between the outer protective skin of the spinal cord (called the dura mater) and the surrounding vertebrae. So the device lies against the spinal cord, and is protected by the bones that make up the spine (as shown in the image below).

stimimplanttrial_1280

The stimulating electrodes within the epidural space. Source: SpineOne

An electrical pulse generator is implanted in the lower abdomen and conducting wires are connected between the electrodes to the generator. Much like deep brain stimulation, the system is entirely enclosed in the body and operated with a remote control.

How does spinal cord stimulation work?

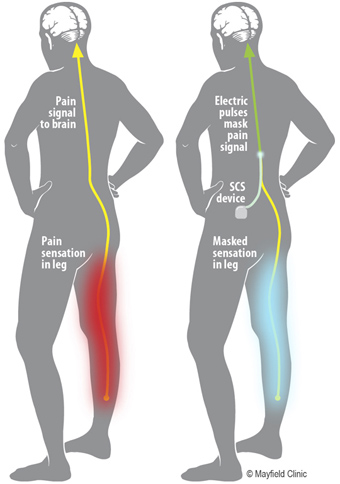
The stimulation basically interrupts the feeling of pain – blocking it from reaching the brain – substituting it with a more pleasing sensation called paresthesia (a kind of tingling or numbness).

PE-SCS Fig1

Source: MayoClinic

The stimulation does not eliminate the source of pain, it simply masks it by interfering with the signal going to the brain.  As a result the amount of relief from pain varies from person to person. In general, spinal cord stimulation resulting in a 50-70% reduction in pain.

But Parkinson’s results from inability to move, how would spinal cord stimulation work in Parkinson’s disease?

Yeah, this is a good question and the answer is not entirely clear, but the researchers (behind the research we discuss below) suggest that beneficial effects from spinal cord stimulation in Parkinson’s disease could be coming from direct activation of ascending pathways reaching thalamic nuclei and the cerebral cortex. That is to say (in plain English): activation of the spinal cord results in a signal going up into the brain where it alters the interaction between two of the regions involved in the initiation of movement (the thalamus and the cortex). And as we shall discuss below, there is evidence backing this idea.

Ok, so how much research has been done on spinal cord stimulation for Parkinson’s disease?

Actually quite a bit (in fact, for a good early review on the topic – click here).

The first real attempt at spinal cord stimulation for Parkinson’s disease was this report here:

Spinal1

Title: Spinal Cord Stimulation Restores Locomotion in Animal Models of Parkinson’s Disease
Authors: Fuentes, R., Petersson, P., Siesser, W. B., Caron, M. G., & Nicolelis, M. A. L.
Journal: Science (2009) 323(5921), 1578-1582.
PMID: 19299613                   (This article is OPEN ACCESS if you would like to read it)

It was conducted by Prof Miguel Nicolelis and his colleagues at Duke University. Duke were kind enough to make this short video about the research:

In their research report, the scientists injected mice with a drug that reduced the level of dopamine in the brain (the tyrosine hydroxylase inhibitor alpha-methyl-para-tyrosine  or AMPT). Similar to Parkinson’s disease, this resulted in a significant reduction in the movements of those mice. It also resulted in changes in the neuronal activity patterns of cells in an area of the brain called the motor cortex (we have talked about the motor cortex in a previous post). When the researchers then conducted spinal cord stimulation on these mice, they found that stimulation corrected both the loss of movement and the altered activity in the motor cortex.

The researchers then tested spinal cord stimulation in rats which had their dopamine system severely depleted (using the neurotoxin 6-OHDA), and they again found that the treatment could rescue the loss of locomotor ability. Curiously, spinal cord stimulation in the rats also caused an increase in locomotion activity after the stimulation period had stopped. On top of this, the researchers found that spinal cord stimulation aided the effect of L-dopa, allowing lower doses of L-dopa to achieve the same behavioural results as higher doses in animals not receiving spinal cord stimulation.

These initial results were then replicated in primates:

Monkey

Title: Spinal cord stimulation alleviates motor deficits in a primate model of Parkinson disease.
Authors: Santana MB, Halje P, Simplício H, Richter U, Freire MA, Petersson P, Fuentes R, Nicolelis MA.
Journal: Neuron. 2014 Nov 19;84(4):716-22.
PMID: 25447740              (This article is OPEN ACCESS if you would like to read it)

In this study, the researchers modelled Parkinson’s disease in five adult marmosets using the neurotoxin 6-OHDA, which resulted in a reduction in spontaneous behaviour and a significant loss of dopamine neurons in the brain. They then implanted a spinal cord stimulator in each of the animals, which once activated resulted in a 200% improvement in some aspects of behavioural activity. Improvements observed in Parkinson’s-like features included freezing (31%), hypokinesia (23%), posture (23%), and bradykinesia (21%) as calculated by investigators blind to the treatment conditions of each subject.

In the brain, the researchers found that spinal cord stimulation resulted in similar improvements in neural activity as that seen with L-dopa treatment. Given all of these results, the investigators concluded that spinal cord stimulation “should be further tested in clinical studies aimed at measuring its long-term efficacy as a less invasive, long-term therapy for” people with Parkinson’s disease.

And it was not just Prof Nicolelis’ group that has achieved these results. Japanese researchers have also reported spinal cord stimulation having beneficial effects in models of Parkinson’s disease:

NeuoroProtect

Title: Spinal cord stimulation exerts neuroprotective effects against experimental Parkinson’s disease.
Authors: Shinko A, Agari T, Kameda M, Yasuhara T, Kondo A, Tayra JT, Sato K, Sasaki T, Sasada S, Takeuchi H, Wakamori T, Borlongan CV, Date I.
Journal: PLoS One. 2014 Jul 10;9(7):e101468.
PMID: 25009993           (This article is OPEN ACCESS if you would like to read it)

In this report, the researchers actually found that spinal cord stimulation resulted in neuroprotection in a classical model of Parkinson’s disease (rodent 6-OHDA striatal delivery). Across three different levels of stimulation, the researchers reported better rescue of motor deficits and protection of dopamine neurons (particularly for 50Hz stimulation). The researchers also provided evidence suggesting that the neuroprotective effect might have something to do with a protein called Vascular endothelial growth factor (or VEGF). Interestingly, they found that the neuroprotective protein GDNF (that we have discussed before – click here for that post) was not involved.

So has this spinal stimulation procedure ever been conducted in humans with Parkinson’s disease before?

Yes, it has. But the results were a bit disappointing.

Stim1

Title: Spinal cord stimulation failed to relieve akinesia or restore locomotion in Parkinson disease.
Authors: Thevathasan W, Mazzone P, Jha A, Djamshidian A, Dileone M, Di Lazzaro V, Brown P.
Journal: Neurology. 2010 Apr 20;74(16):1325-7.
PMID: 20404313          (This article is OPEN ACCESS if you would like to read it)

In this very small clinical study, just two people (both 75+ years of age) with Parkinson’s disease were fitted with spinal cord stimulators. Ten days after the surgery, the subjects participated in a blind analysis of the motor effects of spinal stimulation (blind analysis meaning that the assessors were not aware of their surgical treatment). The assessors, however, found no improvements as a result of the stimulation treatment.

This report lead to a letter to the journal from Prof Nicolelis and his colleagues:

Neurol

In their letter, Prof Nicolelis and co point out several issues with the clinical study that may impact the final results (such as the tiny size of the study (only two participants) and the fact that the electrodes were located at a high cervical level, while in the rodent study they were located at a high thoracic level). In addition, the commercially available electrodes used in the human clinical study did not match the relative size or orientation of the electrodes used in the rodent study.

The researchers of the clinical study suggested that the beneficial motor effect described in the rodent study may be due to an increase in arousal (as a result of higher stimulation). But Prof Nicolelis and colleagues pointed out in their letter that their rodent study included three control experiments (including air puffs, trigeminal stimulation at the highest intensity tolerated by the animals, and direct measurements of changes in heart rate following spinal stimulation) which did not find a strong connection between arousal response and recovery seen in the level of locomotion.

The letter concluded that the results of the small clinical trial were inconclusive, and that further research in nonhuman primate models of Parkinson’s are required to determine the effects of electrode design and stimulation parameters. The doctors behind the clinical study agreed that more research is required.

And what do we know about this new clinical study?

Unfortunately, not very much.

The study is being conducted by Prof. Mandar Jog of Western University. Recently the Parkinson’s Society Southwestern Ontario provided some funding towards the study (Click here for more on this), but that is about as much as we could find on the work.

So what does it all mean?

Summing up: Spinal cord stimulation is a technique that is used to alleviate severe back pain. It has recently been proposed for Parkinson’s disease, resulting in several clinical trials. Here at the SoPD we are not sure what our opinion on spinal cord stimulation is at present, except that more research is obviously required.

If the results from the new clinical study (being conducted in Canada) indicate that spinal cord stimulation has beneficial effects for people with Parkinson’s disease, it would certainly represent a significant step forward for the community which relies heavily on symptom masking drugs at present. Before proceeding to wider clinical availability, however, larger clinical studies will be required to truly demonstrate safety and efficacy.

We’ll let you know if we hear anything else about this developing area of research.


The banner for today’s post was sourced from Greg Dunn

Editorial: Putting 200 years into context

200

Here at the SoPD we understand and are deeply sympathetic to the frustration felt by the Parkinson’s community regarding the idea of ‘200 years and still no cure’.

As research scientists, we are in the trench everyday – fighting the good fight – trying to find ways of alleviating this terrible condition. And some of us are also in the clinics, interacting with sufferers and their families, listening to their stories and trying to help. While we do not deal directly with the day-to-day trials of living with Parkinson’s disease, we are keenly aware of many of the issues and are fully invested in trying to correct this condition.

972px-Paralysis_agitans_(1907,_after_St._Leger)

Source: Wikipedia

We do feel, however, that it is important to put some context into that ‘200 years’ time point that we are observing this week. It is too easy for people to think “wow, 200 years and still no cure?”

In our previous post – made in collaboration with Prof Frank Church of the Journey with Parkinson’s blog – we listed the major historical milestones and discoveries made in the Parkinson’s disease field during the last 200 years.

The most striking feature of that time line, however, is how just little actually happened during the first 100 years.

In fact for most of that period, Parkinson’s disease wasn’t even called ‘Parkinson’s disease’.

Of the 48 events that we covered on that time line, 37 of them have occurred in the last 50 years (26 since 2000).

Taking this line of thought one step further, 2017 is also the 20 year anniversary of the discovery of alpha synuclein‘s association with Parkinson’s disease. And what a remarkable 20 years that has been. In 1997, a group of researcher at the National institute of Health led by Robert Nussbaum reported the first genetic mutation in the alpha synuclein gene that infers vulnerability to Parkinson’s disease.

Since then, we have:

  • identified multiple additional mutations within that same gene that increase the risk of developing Parkinson’s disease.
  • determined which forms of alpha synuclein are toxic.
  • identified alpha synuclein as an important component of Lewy bodies – the dense clusters of protein found in the Parkinsonian brain.
  • discovered numerous methods by which alpha synuclein can be passed between cells – potentially aiding in the spread of Parkinson’s disease.
  • developed and validated models of Parkinson’s disease based on manipulations of alpha synuclein (including numerous genetically engineered mice, viral over-expression models, etc).
  • identified alpha synuclein in the lining of the gut of people with Parkinson’s disease and this has aided us in developing new theories as to how the condition may start.
  • set up and run numerous clinical trials targeting alpha synuclein (and we eagerly await the results of those trials).
  • published over 6200 scientific papers (don’t believe me? Click here) – that’s over 300 publications per year!

PBB_Protein_SNCA_image

Alpha synuclein protein. Source: Wikipedia

And the truly amazing part? All of these particular achievements are only dealing with just the one gene: alpha synuclein.

Since the identification of the alpha synuclein mutations, we have subsequently discovered genetic mutations in over 20 other genes that increase the risk of developing Parkinson’s disease. And we have conducted the same activities/experiments for most of those genes as we have for alpha synuclein.

For example, in 2004 we discovered that people with genetic mutations in a gene called glucocerebrosidase (or GBA) had an increased risk of developing Parkinson’s disease. In 2016, just 12 years after that discovery we have started a clinical trial designed specifically for those people (Click here for more on this).

wwwnew2_0

Source: Parkinson’s UK

We here at the SoPD are fully supportive of campaigns like #WeWontWait, and this post was not written (nor meant to be taken) as an excuse response to the ‘200 years and no cure’ frustration. I can understand how it may be read that way, but I did not know how else to write it. And I thought it needed to be written.

The point of this entire post is that those 200 years need to be put into context.

And while all of these words aren’t going to make life easier for someone living with Parkinson’s to deal with their situation, in addition to raising awareness this week I think it is important for the Parkinson’s community to also understand just how far we have come, and how fast we are currently progressing.

The question can be asked: will this be the last major anniversary we acknowledge with regards to Parkinson’s disease?

I sincerely think that there is cause to hope that it is.


Let me finish with a personal note:

I have a good friend – let’s call him Matt.

As a young boy, Matt remembers his grandfather having Parkinson’s disease. He remembers growing up watching the trials and tribulations that the old man went through with the condition. There were basically no treatment options when Matt’s grandfather was diagnosed and little in the way of support for the family. His grandfather’s body simply froze up as the disease progressed. L-dopa probably only became available to Matt’s grandfather during the latter stages of the disease.

Four years ago Matt’s father was diagnosed with Parkinson’s disease.

Thanks to scientific advances, however, Matt’s dad now has a wide range of treatment options on the medication side of things. The disease can be managed so that he can still play his golf and enjoy his retirement – in a way that his own father never could. He also has numerous surgical options once those medications lose their effectiveness (eg. deep brain stimulation, Pallidotomy, etc). The chances are very likely that Matt’s father will pass on by natural causes before he requires many of those additional options.

This is the progress that we have made.

But there is still a lot of work to be done of course.

During a lunch shortly after his father’s diagnosis, Matt looked squarely across the table at me. Me, the Parkinson’s researcher. All of the usual jovial nature was missing from his face and he simply muttered the words ‘hurry up’.

Whether he was speaking for his father, himself or his own young kids, I understood where his words were coming from and the sentiment.

And, as this post and the previous post point out, we are hurrying up.


The banner for today’s post was sourced from BMO

Milestones in Parkinson’s disease research and discovery

Self-Reflected-in-violets

FrankFor today’s post, we have teamed up with Prof Frank Church from the Journey with Parkinson’s blog to bring readers an ‘Introduction to the historical timeline on Parkinson’s disease’.

The idea for this project started as a conversation between Frank and his partner Barbara during a recent weekend at the beach in North Carolina.

Frank said: “Wouldn’t it be cool to publish a Parkinson’s historical timeline for Parkinson’s awareness month?”

However, to complete this project Frank felt it necessary to bring in some extra help in the form of a Parkinson’s expert.

And when everyone else said they were too busy, Frank contacted us.

Truly flattered, we immediately said yes. And the rest is history.


We are happy to present the milestones in Parkinson’s disease research and discover, though we do apologise to the clinicians, scientists, health-care specialists, and their projects that were not cited here but we limited the timeline to ~50 notations.

Below there are six panels outlining different stages of the history of Parkinson’s disease, and under each of them we have briefly described each of the events in the panel.

We hope you like it.

1817-1919- Milestones in Parkinson’s Disease Research and Discovery (Part 1a: Historical):

Slide1

First description of Parkinson’s disease

In 1811, Mr James Parkinson of no. 1 Hoxton Square (London) published a 66 page booklet called an ‘An Essay on the Shaking Palsy’. At the date of printing, it sold for 3 shillings (approx. £9 or US$12). The booklet was the first complete description of a condition that James called ‘Paralysis agitans’ or shaking palsy. In his booklet, he discusses the history of tremor and distinguishes this new condition from other diseases. He then describes three of his own patients and three people who he saw in the street.

The naming of Parkinson’s disease

Widely considered the ‘Father of modern neurology’, the importance of Jean-Martin Charcot’s contribution to modern medicine is rarely in doubt. From Sigmund Freud to William James (one of the founding fathers of Psychology), Charcot taught many of the great names in the early field of neurology. Between 1868 and 1881, Charcot focused much of his attention on the ‘paralysis agitans’. Charcot rejected the label ‘Paralysis agitans’, however, suggesting that it was misleading in that patients were not markedly weak and do not necessarily have tremor. Rather than Paralysis Agitans, Charcot suggested that Maladie de Parkinson (or Parkinson’s disease) would be a more appropriate name, bestowing credit to the man who first described the condition. And thus 70 years after passing away, James Parkinson was immortalized with the disease named after him.

The further clinical characterisation of Parkinson’s disease

British neurologist Sir William Gowers published a two-volume text called the Manual of Diseases of the Nervous System (1886, 1888). In this book he described his personal experience with 80 people with Parkinson’s disease in the 1880s. He also identified the subtle male predominance of the disorder and provided illustrations of the characteristic posture. In his treatment of Parkinson’s tremor, Gower used hyoscyamine, hemlock, and hemp (cannabis) as effective agents for temporary tremor abatement.

The discovery of the chemical dopamine

In the Parkinsonian brain there is a severe reduction in the chemical dopamine. This chemical was first synthesised in 1910 by George Barger and James Ewens at the Wellcome labs in London, England.

The discovery of Lewy bodies

One of the cardinal features of Parkinson’s disease in the brain is the presence of Lewy bodies – circular clusters of protein. In 1912, German neurologist Friedrich Lewy, just two years out of medical school and still in his first year as Director of the Neuropsychiatric Laboratory at the University of Breslau (now Wroclaw, Poland) Medical School discovered these ‘spherical inclusions’ in the brains of a people who had died with Parkinson’s disease.

The importance of the substantia nigra in Parkinson’s disease

The first brain structure to be associated with Parkinson’s disease was the substantia nigra. This region lies in an area called the midbrain and contains the majority of the dopamine neurons in the human brain. It was in 1919 that a Russian graduate student working in Paris, named Konstantin Tretiakoff, first demonstrated that the substantia nigra was associated with Parkinson’s disease. Tretiakoff also noticed circular clusters in the brains he examined and named them ‘corps de Lewy’ (or Lewy bodies) after the German neurologist Friedrich Lewy who first discovered them.

1953-1968- Milestones in Parkinson’s Disease Research and Discovery (Part 1b: Historical):

Slide2

The first complete pathologic analysis of the Parkinsonian brain

The most complete pathologic analysis of Parkinson’s disease with a description of the main sites of damage was performed in 1953 by Joseph Godwin Greenfield and Frances Bosanquet.

The discovery of a functional role for dopamine in the brain

Until the late 1950s, the chemical dopamine was widely considered an intermediate in the production of another chemical called norepinephrine. That is to say, it had no function and was simply an ingredient in the recipe for norepinephrine. Then in 1958, Swedish scientist Arvid Carlsson discovered that dopamine acts as a neurotransmitter – a discovery that won Carlsson the 2000 Nobel prize for Physiology or Medicine.

The founding of the Parkinson’s Disease Foundation

In 1957, a nonprofit organisation called the Parkinson’s Disease Foundation was founded by William Black. It was committed to finding a cure for Parkinson’s Disease. Since its founding in 1957, PDF has funded more than $115 million worth of scientific research in Parkinson’s disease.

The discovery of the loss of dopamine in the brain of people with Parkinson’s disease

In 1960, Herbert Ehringer and Oleh Hornykiewicz demonstrated that the chemical dopamine was severely reduced in brains of people who had died with Parkinson’s disease.

The first clinical trials of Levodopa

Knowing that dopamine can not enter the brain and armed with the knowledge that the chemical L-dopa was the natural ingredient in the production of dopamine, Oleh Hornykiewicz & Walther Birkmayer began injecting people with Parkinson’s disease with L-dopa in 1961. The short term response to the drug was dramatic: “Bed-ridden patients who were unable to sit up, patients who could not stand up when seated, and patients who when standing could not start walking performed all these activities with ease after L-dopa. They walked around with normal associated movements and they could even run and jump.” (Birkmayer and Hornykiewicz 1961).

The first internationally-used rating system for Parkinson’s disease

In 1967, Melvin Yahr and Margaret Hoehn published a rating system for Parkinson’s disease in the journal Neurology. It involves 5 stages, ranging from unilateral symptoms but no functional disability (stage 1) to confinement to wheel chair (stage 5). Since then, a modified Hoehn and Yahr scale has been proposed with the addition of stages 1.5 and 2.5 in order to help better describe the intermediate periods of the disease.

Perfecting the use of L-dopa as a treatment for Parkinson’s disease

In 1968, Greek-American scientist George Cotzias reported dramatic effects on people with Parkinson’s disease using oral L-dopa. The results were published in the New England Journal of Medicine. and L-dopa becomes a therapeutic reality with the Food and Drug Administration (FDA) approving the drug for use in Parkinson’s disease in 1970. Cotzias and his colleagues were also the first to describe L-dopa–induced dyskinesias.

1972-1997- Milestones in Parkinson’s Disease Research and Discovery (Part 1c: Historical):

Slide3

Levodopa + AADC inhibitors (carbidopa or benserazide)

When given alone levodopa is broken down to dopamine in the bloodstream, which leads to some detrimental side effects.  By including an aromatic amino acid decarboxylase (AADC) inhibitor with levodopa allows the levodopa to get to the blood-brain barrier in greater amounts for better utilisation by the neurons. In the U.S., the AADC inhibitor of choice is carbidopa and in other countries it’s benserazide.

The discovery of dopamine agonists

Dopamine agonists are ‘mimics’ of dopamine that pass through the blood brain barrier to interact with target dopamine receptors. Since the mid-1970’s, dopamine agonists are often the first medication given most people to treat their Parkinson’s; furthermore, they can be used in conjunction with levodopa/carbidopa. The most commonly prescribed dopamine agonists in the U.S. are Ropinirole (Requip®), Pramipexole (Mirapex®), and Rotigotine (Neupro® patch). There are some challenging side effects of dopamine agonists including compulsive behaviour (e.g., gambling and hypersexuality),  orthostatic hypotension, and hallucination.

The clinical use of MAO-B inhibitors

In the late-1970’s, monoamine oxidase-B (MAO-B) inhibitors were created to block an enzyme in the brain that breaks down levodopa. MAO-B inhibitors have a modest effect in suppressing the symptoms of Parkinson’s.  Thus, one of the functions of MAO-B inhibitors is to prolong the half-life of levodopa to facilitate its use in the brain.  Very recently in clinical trials, it’s been shown that MAO-B inhibitors have some neuroprotective effect when used long-term.  The most widely used MAO-B inhibitors in the U.S. include Rasagiline (Azilect) and Selegiline (Eldepryl and Zelpar); MAO-B inhibitors may reduce “off” time and extend “on” time of levodopa.

Fetal Cell transplantation

After successful preclinical experiments in rodents, a team of researchers in Sweden, led by Anders Bjorklund and Olle Lindvall, began the first clinical trials of fetal cell transplantation for Parkinson’s disease. These studies involved taking embryonic dopamine cells and injecting them into the brains of people with Parkinson’s disease. The cells then matured and replaced the cells that had been lost during the progression of the disease.

The discovery of MPTP

In July of 1982, Dr. J. William Langston of the Santa Clara Valley Medical Center in San Jose (California) was confronted with a group of heroin addicts who were completely immobile. A quick investigation demonstrated that the ‘frozen addicts’ had injected themselves with a synthetic heroin that had not been prepared correctly. The heroin contained a chemical called MPTP, which when injected into the body rapidly kills dopamine cells. This discovery provided the research community with a new tool for modelling Parkinson’s disease.

1997-2006- Milestones in Parkinson’s Disease Research and Discovery (Part 1d: Historical):

Slide4

Alpha synuclein becomes the first gene associated with familial cases of Parkinson’s disease and its protein is found in Lewy bodies

In 1997, a group of researchers at the National institute of Health led by Robert Nussbaum reported the first genetic aberration linked to Parkinson’s disease. They had analysed DNA from a large Italian family and some Greek familial cases of Parkinson’s disease, and they

The gene Parkin becomes the first gene associated with juvenile Parkinson’s disease

The gene Parkin provides the instructions for producing a protein that is involved with removing rubbish from within a cell. In 1998, a group of Japanese scientists identified mutations in this gene that resulted in affected individuals being vulnerable to developing a very young onset (juvenile) version of Parkinson’s disease.

The first use of PET scan brain imaging for Parkinson’s disease

Using the injection of a small amount of radioactive material (known as a tracer), the level of dopamine present in an area of the brain called the striatum could be determined in a live human being. Given that amount of dopamine in the striatum decreases over time in Parkinson’s disease, this method of brain scanning represented a useful diagnostic aid and method of potentially tracking the condition.

The launch of Michael J Fox Foundation

In 1991, actor Michael J Fox was diagnosed with young-onset Parkinson’s disease at 29 years of age. Upon disclosing his condition in 1998, he committed himself to the campaign for increased Parkinson’s research. Founded on the 31st October, 2000, the Michael J Fox Foundation has funded more than $700 million in Parkinson’s disease research, representing one of the largest non-governmental sources of funding for Parkinson’s disease.

The Braak Staging of Parkinson’s pathology

In 2003, German neuroanatomist Heiko Braak and colleagues presented a new theory of how Parkinson’s disease spreads based on the postmortem analysis of hundreds of brains from people who had died with Parkinson’s disease. Braak proposed a 6 stage theory, involving the disease spreading from the brain stem (at the top of the spinal cord) up into the brain and finally into the cortex.

The gene DJ1 is linked to early onset PD

DJ1 (also known as PARK7) is a protein that inhibits the aggregation of Parkinson’s disease-associated protein alpha synuclein. In 2003, researchers discovered mutations in the DJ1 gene that made people vulnerable to a early-onset form of Parkinson’s disease.

The first GDNF clinical trial indicates neuroprotection in people with Parkinson’s disease

A small open-label clinical study involving the direct delivery of the chemical Glial cell-derived neurotrophic factor (GDNF) into the brains of people with Parkinson’s disease indicated that neuroprotection. The subjects involved in the study exhibited positive responses to the treatment and postmortem analysis of one subjects brain indicated improvements in the brain.

The genes Pink1 and LRRK2 are associated with early onset PD

Early onset Parkinson’s is defined by age of onset between 20 and 40 years of age, and it accounts for <10% of all patients with Parkinson’s.  Genetic studies are finding a causal association for Parkinson’s with five genes: alpha synuclein (SNCA), parkin (PARK2), PTEN-induced putative kinase 1 (PINK1), DJ-1 (PARK7), and Leucine-rich repeat kinase 2 (LRRK2). However it happens, and at whatever age it occurs, there is no doubt that genetics and environment combine together to contribute to the development of Parkinson’s.

The discovery of induced pluripotent stem (IPS) cells

In 2006, Japanese researchers demonstrated that it was possible to take skin cells and genetically reverse engineer them into a more primitive state – similar to that of a stem cell. This amazing achievement involved a fully mature cell being taken back to a more immature state, allowing it to be subsequently differentiated into any type of cell. This research resulted in the discoverer, Shinya Yamanaka being awarded the 2012 Nobel prize for Physiology or Medicine.

2007-2016- Milestones in Parkinson’s Disease Research and Discovery (Part 1e: Historical):

Slide5

The introduction of the MDS-UPDRS revised rating scale

The Movement Disorder Society (MDS) unified Parkinson’s disease rating scale (UPDRS) was introduced in 2007 to address two limitations of the previous scaling system, namely a lack of consistency among subscales and the low emphasis on the non-motor features. It is now the most commonly used scale in the clinical study of Parkinson’s disease.

The discovery of Lewy bodies in transplanted dopamine cells

Postmortem analysis of the brains of people with Parkinson’s disease who had fetal cell transplantation surgery in the 1980-1990s demonstrated that Lewy bodies are present in the transplanted dopamine cells. This discovery (made by three independent research groups) suggests that Parkinson’s disease can spread from unhealthy cells to healthy cells. This finding indicates a ‘prion-like’ spread of the condition.

SNCA, MAPT and LRRK2 are risk genes for idiopathic Parkinson’s disease

Our understanding of the genetics of Parkinson’s is rapidly expanding. There is recent evidence of multiple genes linked to an increase the risk of idiopathic Parkinson’s. Interestingly, microtubule-associated protein tau (MAPT) is involved in microtubule assembly and stabilization, and it can complex with alpha synuclein (SNCA).  Future therapies are focusing on  the reduction and clearance of alpha synuclein and inhibition of Lrrk2 kinase activity.

IPS derived dopamine neurons from people with Parkinson’s disease

The ability to generate dopamine cells from skin cells derived from a person with Parkinson’s disease represents not only a tremendous research tool, but also opens the door to more personalized treatments of suffers. Induced pluripotent stem (IPS) cells have opened new doors for researchers and now that we can generate dopamine cells from people with Parkinson’s disease exciting opportunities are suddenly possible.

Neuroprotective effect of exercise in rodent Parkinson’s disease models

Exercise has been shown to be both neuroprotective and neurorestorative in animal models of Parkinson’s. Exercise promotes an anti-inflammatory microenvironment in the mouse/rat brain (this is but one example of the physiological influence of exercise in the brain), which helps to reduce dopaminergic cell death.  Taking note of these extensive and convincing model system results, many human studies studying exercise in Parkinson’s are now also finding positive benefits from strenuous and regular exercise to better manage the complications of Parkinson’s.

Transeuro cell transplantation trial begins

In 2010, a European research consortium began a clinical study with the principal objective of developing an efficient and safe treatment methodology fetal cell transplantation in people with Parkinson’s disease. The trial is ongoing and the subjects will be followed up long term to determine if the transplantation can slow or reverse the features of Parkinson’s disease.

Successful preclinical testing of dopamine neurons from embryonic stem cells

Scientists in Sweden and New York have successfully generated dopamine neurons from human embryonic stem cells that can be successfully transplanted into animal models of Parkinson’s disease. Not only do the cells survive, but they also correct the motor deficits that the animals exhibit. Efforts are now being made to begin clinical trials in 2018.

Microbiome of the gut influences Parkinson’s disease

Several research groups have found the Parkinson’s disease-associated protein alpha synuclein in the lining of the gut, suggesting that the intestinal system may be one of the starting points for Parkinson’s disease. In 2016, researchers found that the bacteria in the stomachs of people with Parkinson’s disease is different to normal healthy individuals. In addition, experiments in mice indicated that the bacteria in the gut can influence the healthy of the brain, providing further evidence supporting a role for the gut in the development of Parkinson’s disease.

2016-2017- Milestones in Parkinson’s Disease Research and Discovery (Part 2: Clinical trials either recently completed or in progress)

Slide6

Safety, Tolerability and Efficacy Assessment of Dynacirc (Isradipine) for PD (STEADY-PD) III trial

Isradipine is a calcium-channel blocker approved for  treating high blood pressure; however, Isradipine is not approved for treating Parkinson’s. In animal models, Isradipine has been shown to slow the progression of PD by protecting dopaminergic neurons.  This study is enrolling newly diagnosed PD patients not yet in need of symptomatic therapy. Participants will be randomly assigned Isradipine or given a placebo.

Treatment of Parkinson’s Psychosis with Nuplazid

Approximately 50% of the people with Parkinson’s develop psychotic tendencies. Treatment of their psychosis can be relatively difficult. However, a new drug named Nuplazid was recently approved by the FDA specifically designed to treat Parkinson’s psychosis.

Opicapone (COMT Inhibitor) as Adjunct to Levodopa Therapy in Patients With Parkinson Disease and Motor Fluctuations

Catechol-O-methyl transferase (COMT) inhibitors prolong the effect of levodopa by blocking its metabolism. COMT inhibitors are used primarily to help with the problem of the ‘wearing-off’ phenomenon associated with levodopa. Opicapone is a novel, once-daily, potent third-generation COMT inhibitor.  It appears to be safer than existing COMT drugs. If approved by the FDA, Opicapone is planned for use in patients with Parkinson’s taking with levodopa who experience wearing-off issues.

Nilotinib (Tasigna® by Novartis) indicates positive results in phase I trial.

Nilotinib is a drug used in the treatment of leukemia. In 2015, it demonstrated beneficial effects in a small phase I clinical trial of Parkinson’s disease. Researchers believe that the drug activates the disposal system of cells, thereby helping to make cells healthier. A phase II trial of this drug to determine how effective it is in Parkinson’s disease is now underway.

ISCO cell transplantation trial begins

International Stem Cell Corporation is currently conducting a phase I clinical cell transplantation trial at a hospital in Melbourne, Australia. The company is transplanting human parthenogenetic stem cells-derived neural stem cells into the brains of people with Parkinson’s disease. The participants will be assessed over 12 months to determine whether the cells are safe for use in humans.

Neuropore’s alpha-synuclein stabilizer (NPT200-11) passes phase I trial

Neuropore Therapies is a biotech company testing a compound (NPT200-11) that inhibits and stablises the activity of the Parkinson’s disease-associated protein alpha synuclein. This alpha-synuclein inhibitor has been shown to be safe and well tolerated in humans in a phase I clinical trial and the company is now developing a phase II trial.

mGluR4 PAM  (PXT002331) well tolerated in phase I trial

Prexton Therapeutics recently announced positive phase I clinical trial results for their lead drug, PXT002331, which is the first drug of its kind to be tested in Parkinson’s disease. PXT002331 is a mGluR4 PAM – this is a class of drug that reduces the level of inhibition in the brain. In Parkinson’s disease there is an increase in inhibition in the brain, resulting in difficulties with initiating movements. Phase II clinical trials to determine efficacy are now underway.

Initial results of Bristol GDNF trial indicate no effect

Following remarkable results in a small phase I clinical study, the recent history of the neuroprotective chemical GDNF has been less than stellar. A subsequent phase II trial demonstrated no difference between GDNF and a placebo control, and now a second phase II trial in the UK city of Bristol has reported initial results also indicating no effect. Given the initial excitement that surrounded GDNF, this result has been difficult to digest. Additional drugs that behave in a similar fashion to GDNF are now being tested in the clinic.

Immunotherapies proves safe in phase I trials (AFFiRis & Prothena)

Immunotherapy is a treatment approach which strengthens the body’s own immune system. Several companies (particularly ‘AFFiRis’ in Austria and ‘Prothena’ in the USA) are now conducting clinical trials using treatments that encourage the immune system to target the Parkinson’s disease-associated protein alpha synuclein. Both companies have reported positive phase I results indicating the treatments are well tolerable in humans, and phase II trials are now underway.

Living Cell Technologies Limited continue Phase II trial of NTCELL

A New Zealand company called Living Cell Technologies Limited have been given permission to continue their phase II clincial trial of their product NTCELL, which is a tiny capsule that contains cells which release supportive nutrients when implanted in the brain. The implanted participants will be blindly assessed for 26 weeks, and if the study is successful, the company will “apply for provisional consent to treat paying patients in New Zealand…in 2017”.

MAO-B inhibitors shown to be neuroprotective.

MAO-B inhibitors block/slow the break down of the chemical dopamine. Their use in Parkinson’s disease allows for more dopamine to be present in the brain. Recently, several longitudinal studies have indicated that this class of drugs may also be having a neuroprotective effect.

Inhalable form of L-dopa

Many people with Parkinson’s disease have issues with swallowing. This makes taking their medication in pill form problematic. Luckily, a new inhalable form of L-dopa will shortly become available following recent positive Phase III clinical trial results, which demonstrated a statistically significant improvements in motor function for people with Parkinson’s disease during OFF periods.

Exenatide trial results expected

Exenatide is a drug that is used in the treatment of diabetes. It has also demonstrated beneficial effects in preclinical models of Parkinson’s disease, as well as an open-label clinical study over a 14 month period. Interestingly, in a two year follow-up study of that clinical trial – conducted 12 months after the patients stopped receiving Exenatide – the researchers found that patients previously exposed to Exenatide demonstrated significant improvements compared to how they were at the start of the study. There is currently a placebo-controlled, double blind phase II clinical trial being conducted and the results should be reported before the end of 2017.


A personal reflection

As I suggested at the start of this post, this endeavour was entirely Frank’s idea – full credit belongs with him. I was more than happy to help him out with it though as I thought it was a very worthy project. During this 200 year anniversary, I believe it is very important to acknowledge just how far we have come in our understanding of Parkinson’s disease since James first put pen to paper and described the six cases he had seen in London.

And Frank’s idea perfectly captures this.


The banner for today’s post was sourced from Greg Dunn (we are big fans!)

The Journal of Parkinson’s disease – special issue

JPD_logo_editors

Our policy at the SoPD is not to advertise or endorse commercial products or services. This is to avoid any ethical or conflict of interest situations.

Every now and then, however, we see something that we believe will be of interest and value to the Parkinson’s community…aaand we bend our policy rule book.


Today the Journal of Parkinson’s disease released a “200 years of Parkinson’s disease” OPEN ACCESS special issue of their journal which highlights some of the major discoveries in the field of Parkinson’s disease research.

Critically, the articles provide insights into how the discoveries were made, and they are written by some of the biggest names in the Parkinson’s research community (many of whom were actually there when the discoveries were made).

The issue has articles dealing with topics including:

Click here to see all of the articles in this special issue.

We fully recommend readers take advantage of this OPEN ACCESS issue and learn about how some of these great discoveries were made.

Happy reading.


Full disclosure: The Journal of Parkinson’s disease is a product of IOS Press. The SoPD has not been approached by or made any offers to IOS Press or anyone at the Journal of Parkinson’s disease. We merely thought that the material in this particular OPEN ACCESS issue would be of interest to our readers.


The banner for today’s post was sourced from the Journal of Parkinson’s disease

New kiwi research in Parkinson’s disease

0f6b3c3205fbdc30c9216c205d1bc039

I really didn’t expect to be writing about Parkinson’s research being conducted in New Zealand again so quickly, but yesterday a new study was published which has a few people excited.

It presents evidence of how the disease may be spreading… using cells collected from people with Parkinson’s disease.

In today’s post we will review the study and discuss what it means for Parkinson’s disease.


022217_ts_zealandia_main_free

The South Island of NZ from orbit. Source: Sciencenews

We may have mentioned the protein Alpha synuclein once or twice on this blog.

For anyone familiar with the biology of Parkinson’s disease, alpha synuclein is a major player. It is either public enermy no.1 in the underlying pathology of this condition or else it is the ultimate ‘fall guy’, left standing in the crime scene holding the bloody knife.

Remind me, what is alpha synuclein?

Alpha synuclein is an extremely abundant protein in our brains – making up about 1% of all the proteins floating around in each neuron (one of the main types of cell in the brain).

In healthy brain cells, normal alpha synuclein is typically found just inside the surface of the membrane surrounding the cell body and in the tips of the branches extending from the cell (in structures called presynaptic terminals which are critical to passing messages between neurons).

And why is alpha synuclein important in Parkinson’s disease?

Genetic mutations account for 10-20% of the cases in Parkinson’s disease.

Five mutations in the alpha-synuclein gene have been identified which are associated with increased risk of Parkinson’s disease (A53T, A30P, E46K, H50Q, and G51D – these are coordinates for locations on the alpha synuclein gene). Rare duplication or triplication of the gene have also been associated with  Parkinson’s disease.

biomolecules-05-00865-g001

The structure of alpha synuclein protein – blue squares are mutations. Source: Mdpi

So genetically, alpha synuclein is associated with Parkinson’s disease. But it is also involved at the protein level.

In brains of many people with Parkinson’s disease, there are circular clumps of alpha synuclein (and other proteins) that collect inside cells. These clumps are called Lewy bodies. They are particularly abundant in areas of the brain that have suffered cell loss.

Fig2_v1c

A lewy body (brown with a black arrow) inside a cell. Source: Cure Dementia

No one has ever seen the process of Lewy body formation, so all we can do is speculate about how these aggregates develop. Currently there is a lot of evidence supporting the idea that alpha synuclein can be passed between cells. Once inside the new cell, the alpha synuclein helps to seed the formation of new Lewy bodies, and this is how the disease is believed to progress.

Mechanism of syunuclein propagation and fibrillization

The passing of alpha synuclein between brain cells. Source: Nature

Exactly how alpha synuclein is being passed between cells is the topic of much research at the moment. There are many theories and some results implicating methods such as direct penetration, or via a particular receptor. Perhaps even by a small package called an exosome being passed between cells (see image above).

How this occurs in the Parkinson’s disease brain, however, is unknown.

And this (almost) brings us to the kiwi scientists.

Last years, a group of Swiss scientists demonstrated that alpha synuclein could be passed between cells via ‘nanotubes’ – tiny tubes connecting between cells. The outlined their observations and results in this article:

switzerland
Title: Tunneling nanotubes spread fibrillar α-synuclein by intercellular trafficking of lysosomes.
Authors: Abounit S, Bousset L, Loria F, Zhu S, de Chaumont F, Pieri L, Olivo-Marin JC, Melki R, Zurzolo C.
Journal: EMBO J. 2016 Oct 4;35(19):2120-2138.
PMID: 27550960

The researchers who conducted this study were interested in tunneling nanotubes.

Yes, I know, ‘What are tunneling nanotubes?’

Tunneling nanotubes (also known as Membrane nanotubes or cytoneme are long protrusions extending from one cell membrane to another, allowing the two cells to share their contents. They can extend for long distances, sometimes over 100 μm – 0.1mm, but that’s a long way in the world of cells!

nanotubes

Tunneling nanotubes (arrows). Source: Wikipedia (and PLOSONE)

Previous studies had demonstrated that tunneling nanotubes can pass different infectious agents (HIV for example – click here to read more on this), supporting the idea that these structures could be a general conduit by certain diseases could be spreading.

nanotubes

A tunneling nanotube between two cells. Source: Pasteur

In their study the Swiss researchers found that alpha synuclein could be transferred between brain cells (grown in culture) via tunneling nanotubes. In addition, following that process of transfer, the alpha synuclein was able to induce the aggregation (or clumping) of the alpha synuclein in recipient cells.

A particularly interesting finding was that alpha synuclein appeared to encourage the appearance of tunneling nanotubes (there were more tunneling nanotubes apparent when cells produced more alpha synuclein). And the alpha synuclein that was being transferred was being passed on in ‘lysosomal vesicles’ – these are the rubbish bags of the cell (lysosomal vesicles are used to take proteins away for degradation).

Paints a rather insidious picture of the ‘ultimate fall guy’ huh!

And that image was made worse by the results published by the kiwis last night:

maurice

Title: α-synuclein transfer through tunneling nanotubes occurs in SH-SY5Y cells and primary brain pericytes from Parkinson’s disease patients
Authors: Dieriks BV, Park TI, Fourie C, Faull RL, Dragunow M, Curtis MA.
Journal: Scientific Reports, 7, Article number: 42984
PMID: 28230073                    (This article is OPEN ACCESS if you would like to read it)

In their study, the New Zealand scientists extended the Swiss research by looking at cells collected from people with Parkinson’s disease. The researchers took human brain pericytes, which were derived from the postmortem brains of people who died with Parkinson’s disease.

And before you ask: pericytes are cells that wrap around the cells lining small blood vessels. They are important to the development of new blood vessels and maintaining the structural integrity of microvasculature.

aa-pericit4ub6b

A pericyte (blue) hugging a blood vessel (red). Source: Xvivo

Pericytes contain alpha synuclein precipitates like those seen in neurons, and the kiwi scientists demonstrated that pericytes too can transfer alpha synuclein via tunneling nanotubes to neighbouring cells – representing a non-neuronal method of transport.

They also found that the transfer through the tunneling nanotubes can be very rapid – within 30 seconds – and the transferred alpha synuclein can hang around for more than 72 hours, suggesting that it is difficult for the receiving cell to dispose of. The researchers did note that the transfer through tunneling nanotubes occurred only in small subset of cells, but that this could explain the slow progression of Parkinson’s disease over time.

What does it all mean?

In order for us to truly tackle Parkinson’s disease and bring it under control, we need to know how this slowly progressing neurodegenerative condition is spreading. Some researchers in New Zealand have provided evidence involving cells collected from people with Parkinson’s disease that indicates one method by which the disease could be passed from one cell to another.

Tiny tunnels between cells, allowing material to be shared, could explain how the disease slowly progresses. The scientists observed the Parkinson’s associated protein alpha synuclein being passed between cells and then hanging around for more than a few days.

This method of transfer was made more interesting because the New Zealand researchers reported that non-neuronal cells (Pericytes, collected from people with Parkinson’s disease) could also form tunneling nanotubes. This observation raises questions as to what role non-neuronal cells could be playing in Parkinson’s disease.

This line of questions will obviously be followed up in future research, as will efforts to determine if tunneling nanotubes are actually present in the human brain or simply biological oddities present only in the culture dish. Demonstrating nanotubes in the brain will be difficult, but it would provide us with solid evidence that this method of disease transfer could be a bonafide cause of disease spread.

We watch with interest for further work in this area.


FULL DISCLOSURE: The author of this blog is a kiwi… and proud of it. He is familiar with the researchers who have conducted this research, but has had no communication with them regarding the publishing of this post. He simply thought that the results of their study would be of interest to the Parkinson’s community.


The banner for today’s post was sourced from Pinterest

PARIS is always a good idea

bzn8qhy

Audrey Hepburn was taking about the city when she uttered the words that title this post, but today we will be talking about the protein that bears the same name: PARIS.

Last week new research was published which demonstrated that in the absence of Parkin and Pink1 protein, the protein PARIS builds up and becomes toxic for cells.

Today’s post will review that research and we’ll discuss what it all means for Parkinson’s disease.


paris

No label required. A magnificent city. Source: HathawaysofHaworth

Today’s post has nothing to do with the city of Paris, but it is always nice to have photos of this European capital gracing the page.

We have recently discussed the Parkinson’s associated proteins Pink1 and Parkin (click here for that post). Today we will be revisiting these proteins as we discuss another protein that they interact with: PARIS (specifically PARIS1).

What is PARIS?

PARIS (aka TBC1D2 or TBC1 Domain Family Member 2) is a GTPase-activating protein.

What does that mean?

Getting a signal from outside of a cell into the interior is a complicated affair. There are numerous ways to do it, but one of the most common involves ‘G-proteins‘. These are involved with transmitting a signal from the outside of a cell into the interior, and when inside the cell G-proteins act as molecular switches.

G-proteins are located inside the cell membrane and are activated by G-protein-coupled receptors. When a signaling molecule binds to the G-protein-coupled receptor on the outside of the cell membrane, the portion of the receptor inside the cell activates the G-protein which then starts of a chain of events resulting in the signal being passed on.

11_07bgprotcoupledrec-l

Source: Bio1151

The role of GTPase-Activating Proteins in this process is to turn the G protein’s activity off. In step 4 of the image above, a GTPase-Activating Protein (which is not shown) binds to the G-protein and terminate the activity of the signalling event – returning it to an inactive state.

Thus, GTPase-Activating Proteins – like PARIS – are important regulators of signalling inside the cell.

What do we know about PARIS1 in Parkinson’s disease?

So a few years ago, a group of researchers led by Prof Ted Dawson at John Hopkins School of Medicine published this study:

cell

Title: PARIS (ZNF746) repression of PGC-1α contributes to neurodegeneration in Parkinson’s disease.
Authors: Shin JH, Ko HS, Kang H, Lee Y, Lee YI, Pletinkova O, Troconso JC, Dawson VL, Dawson TM.
Journal: Cell. 2011 Mar 4;144(5):689-702.
PMID: 21376232        (This article is OPEN ACCESS if you would like to read it)

In this study, the researchers noticed that the protein PARIS was accumulating in cells that did not have the Parkinson’s associated protein, Parkin. In those cells, the Parkin gene was mutated so that the Parkin protein was not produced properly. The researchers discovered that Parkin was important for labelling old PARIS protein for disposal. Thus in the absence of Parkin, PARIS protein would not be disposed of and simply piled up.

This build up of PARIS resulted in the loss of dopamine neurons in mice that did not produce Parkin. When the researchers re-introduced normal Parkin protein, the researchers were able to rescue the cell loss. Interestingly, the researchers also found that over production of PARIS in normal mice resulted in cell loss which could be rescued by a similar over production of Parkin.

When they looked in postmortem human brains, the researchers found that levels of PARIS protein were more than two times higher in regions affected by Parkinson’s disease (the striatum and the substantia nigra) of people with sporadic Parkinson’s disease when compared to healthy controls. Interestingly, this increase was only seen with PARIS protein, and not PARIS RNA (where the scientists saw no different with control samples), suggesting a build up of PARIS protein in the Parkinsonian brain.

The investigators concluded that this meant PARIS was could be playing a role in the cell loss associated with Parkinson’s disease.

They followed up this research a few years later with this publication:

parkins

Title: Parkin loss leads to PARIS-dependent declines in mitochondrial mass and respiration.
Authors: Stevens DA, Lee Y, Kang HC, Lee BD, Lee YI, Bower A, Jiang H, Kang SU, Andrabi SA, Dawson VL, Shin JH, Dawson TM.
Journal: Proc Natl Acad Sci U S A. 2015 Sep 15;112(37):11696-701.
PMID: 26324925     (This article is OPEN ACCESS if you would like to read it)

In this study, the same researchers found that when they remove the Parkin protein from the brains of adult mice there would be a decrease in the size and number of mitochondria. We have previous discussed mitochondria – the power stations of the cell – and their loss is bad news for a cell (click here to read more on mitochondria).

The researchers next demonstrated that this loss of mitochondria could reversed by removing PARIS protein from the Parkin mutant mice, and this prevented the loss of dopamine neurons. They also showed that the loss of mitochondria (and loss of dopamine neurons) could be caused by over production of PARIS in normal mice.

These results pointed towards an important role for both Parkin and PARIS in the maintenance of healthy mitochondria.

So what new research has been published about PARIS1?

This study was published last week:

dawson

Title: PINK1 Primes Parkin-Mediated Ubiquitination of PARIS in Dopaminergic Neuronal Survival.
Authors: Lee Y, Stevens DA, Kang SU, Jiang H, Lee YI, Ko HS, Scarffe LA, Umanah GE, Kang H, Ham S, Kam TI, Allen K, Brahmachari S, Kim JW, Neifert S, Yun SP, Fiesel FC, Springer W, Dawson VL, Shin JH, Dawson TM.
Journal: Cell Rep. 2017 Jan 24;18(4):918-932.
PMID: 28122242       (This article is OPEN ACCESS if you would like to read it)

In their study the researchers found that Parkin is not the only Parkinson’s associated protein in the PARIS story.

We have previously talked about the protein Pink1 (click here to read more on) – and yes, you would be forgiven if you start to think that all Parkinson’s related proteins start with the latter ‘P’. Pink1 grabs Parkin and causes it to bind to dysfunctional mitochondria. Parkin then signals to the rest of the cell for that particular mitochondria to be disposed of. In this study, the researchers found that Pink1 also grabs PARIS and signals for Parkin to dispose of it. In the absence of Pink1, normal Parkin protein does not label old PARIS protein for disposal and PARIS starts to pile up.

The researchers then began manipulating the levels of Pink in the brains of mice and they observed PARIS-dependent cell loss – that is to say, in the absence of Pink1, cells died only when PARIS was present.

These findings suggest that therapies targeting PARIS could be used in people with Parkinson’s disease who are carrying either a Parkin or a Pink1 mutation (both very common in early onset Parkinson’s disease).

What does it all mean?

People with early onset Parkinson’s disease quite often have a genetic mutation in one of a small number of genes – Pink1 and Parkin being prominent amongst these genes. The researchers who conducted the study that we have reviewed today have identified a common mechanism by which both of these proteins could be acting in their roles in Parkinson’s disease: a protein called PARIS.

Currently there is no treatment (that we are aware of) that targets the PARIS protein – nothing in the clinic nor being experimentally tested. Obviously, however, PARIS represents a VERY interesting protein for further investigations. The Dawson lab has several patents on PARIS (Click here and here for more on these), so evidently people will be working on drug candidates that inhibit PARIS.

There is a naturally occurring inhibitor, a micro RNA cluster miR-17-92 (also known as oncomir-1), which reduces the production of PARIS protein by blocking PARIS RNA (Click here for more on this). Using this micro RNA to target PARIS will be very difficult (both activating/delivering the micro RNA and unknown off target effects).

We are assuming that Prof Dawson and colleagues are rapidly screening compounds to determine which can block or inhibit PARIS activity and we will eagerly wait to see the results of that work.

Watch this space.


The banner for today’s post was sourced from Wallpapercave


EDITORIAL NOTE: Yay, 100 posts!